Check for post-exertional malaise first
PEM is common in long COVID (58.7% in one online survey), and it changes what's safe. Our exercise for long COVID guide has a 5-question check.
Pilates guide
With long COVID, the first question isn't which Pilates, but whether you get post-exertional malaise (PEM): a worsening of your symptoms after even small physical, mental, emotional or social effort, often a day or two later. If you do, pacing comes first. The World Health Organization (WHO) and World Physiotherapy advise against graded exercise and fixed increases, and the National Institute for Health and Care Excellence (NICE) says people with this pattern in ME/CFS shouldn't push through their symptoms. Pilates can then only fit inside a paced day, as a few gentle moves lying or seated.
Without PEM, and once chest pain, breathlessness and palpitations have been checked, Pilates can be part of a cautious return to activity. Two small trials found less fatigue and better walking after Pilates, but neither checked for PEM.
This guide covers PEM and pacing, what the trials show, breathing, dizziness on standing, the moves to use and leave out, and when to stop and get help. There's no class to follow here, for the reasons NICE and the WHO give, and nothing here is a cure.
PEM is common in long COVID (58.7% in one online survey), and it changes what's safe. Our exercise for long COVID guide has a 5-question check.
No graded exercise, no fixed increases, no general programmes, and never push through. Pacing isn't a cure, and nothing here promises recovery.
The NHS says "do not start exercising again before talking to a GP or specialist". Chest pain, breathlessness, palpitations and dizziness need checking first.
They reported less fatigue and better walking, but neither screened for PEM, and recorded online Pilates did nothing in one of them.
The WHO describes "a cautious return to symptom-titrated physical exercise training". Start with a short lying and seated routine, keep the same amount for at least a week, and judge each session over the next 2 to 3 days.
Source 4
You may be more likely to have postural tachycardia syndrome (PoTS) with long COVID. Our Pilates for POTS guide has a class that never asks you to stand.
Source 8
The NHS uses long COVID for symptoms that last longer than 12 weeks after COVID-19. NICE calls symptoms from 4 to 12 weeks "ongoing symptomatic COVID-19" and after 12 weeks "post-COVID-19 syndrome". The most common are extreme tiredness, shortness of breath, joint and muscle pain and brain fog. The NHS says "You may find your symptoms get worse if you're stressed or have been more active", and "There's currently no cure for long COVID". The WHO estimates that about 6 in 100 people who have COVID-19 develop it.
NICE defines it as "The worsening of symptoms that can follow minimal cognitive, physical, emotional or social activity, or activity that could previously be tolerated". The WHO says it can come 12 to 72 hours after activity, and that people may not mention it unless asked. World Physiotherapy's list of triggers includes a shower, a social activity, walking, reading, an emotional conversation, or a loud or bright room. It's also called post-exertional symptom exacerbation (PESE).
In an online survey of 213 people with long COVID, 58.7% met the PEM thresholds of a questionnaire used in ME/CFS (a self-selected group). In 25 people with long COVID and PEM, one all-out cycling test brought on PEM in all of them, with symptoms for up to 7 days and more muscle damage the next day.
North Bristol NHS Trust describes it as "when your body has adapted to a particular way of breathing due to stressors or triggers, which means your body has lost its natural rhythm": upper-chest or mouth breathing, over-breathing, frequent sighing and yawning, and breathlessness on little exercise. A physiotherapist can treat it.
Source 13
Getting there, getting down to and up from the floor, following spoken cues and counts, talking, light and music all use energy; classical classes string 20 or more moves together with few rests; and standing work and quick changes between the floor and standing are hard with PoTS (our reading, from the symptoms NICE and the NHS list).
Our exercise for long COVID guide has a 5-question check, adapted from the DePaul questionnaire used in ME/CFS. If any of its signs happen about half the time or more and bother you moderately or more, treat it as PEM and talk to your GP or long COVID team. It was tested in ME/CFS, not long COVID.
With PEM, a Pilates class or course is the kind of general programme NICE advises against in ME/CFS, and the WHO says rehabilitation based on fixed increases or graded exercise "should not be offered to people experiencing PESE".
PEM typically comes 12 to 48 hours after activity (NICE) or 12 to 72 hours (WHO), so feeling fine straight after a session doesn't mean it was fine.
NICE says activity "is never automatically increased", and rules out programmes with fixed step-by-step increases, "for example, graded exercise therapy". World Physiotherapy says "Graded exercise therapy or fixed activity prescription should not be used" with post-exertional symptoms.
That's World Physiotherapy's advice with PEM, and it adds that "Pacing is not an activity avoidance strategy": you plan activity within your energy limits, with rest built in, and adjust it day by day.
NICE says energy management "is not curative". This page doesn't promise recovery: pacing aims to keep you within your limits so crashes are less likely.
Source 3
In the RECOVER-ENERGIZE pacing trial (300 US adults with PEM after COVID-19), 12 weekly sessions with a pacing coach reduced how often and how badly PEM struck, by about half a point on a 0 to 4 scale at 12 weeks, more than PEM education with weekly support calls. These results are posted on the trial registry and haven't been peer reviewed. An earlier trial of a pacing app with an activity tracker (250 people) found no difference in PEM.
It asks for a personalised rehabilitation plan after symptoms that could affect safe rehabilitation have been investigated, and lists "What is the clinical effectiveness of exercise interventions for people with post-COVID-19 syndrome?" as a research question. It doesn't mention graded exercise or PEM, so where PEM is present this page follows NICE's ME/CFS guideline, as our exercise for long COVID guide does.
A 2026 international guideline suggests personalised rehabilitation only after screening "to exclude those with post-exertional malaise", with activity management first for people who have it. A 2025 American Heart Association statement argues that lost fitness plays a major role and that tailored training may help. That isn't the NICE, WHO or World Physiotherapy position for people with PEM, and this page follows NICE.
Two small Pilates trials in long COVID, neither of which screened for post-exertional malaise. The wider rehabilitation trials rarely checked for it either.
In Brazil, adults with fatigue at least 3 months after COVID-19 did 12 weeks of mat Pilates 3 times a week for 50 minutes, face to face or by recorded online video, or followed a stretching booklet. Only face-to-face Pilates improved fatigue, walking distance (463 to 514 metres) and some strength measures; the online version changed nothing. There were 21 dropouts, side effects weren't reported, people with any functional limitation were excluded, and the paper doesn't mention PEM, PoTS or oxygen drops on exertion. An independent database rated it 5 out of 10.
Twice a week for 8 weeks, against supervised general exercise or no exercise: only Pilates improved walking distance, breathlessness and fatigue after the walk test, and sleep. We could read only the summary, which doesn't say who was included, whether PEM was screened, which exercises were used or what side effects there were.
Source 7
In 48 survivors of severe COVID-19 who had needed a ventilator, equipment Pilates added to pulmonary rehabilitation improved walking (54 against 12 metres) and strength more than rehabilitation alone, in a master's dissertation that hasn't been peer reviewed (we read its summary). In 45 people after intensive care, lung function rose by 21% to 35% with Pilates or aqua-Pilates in 8 weeks, a far bigger effect than exercise usually has on lung function (our reading). Neither checked for PEM.
A 2026 review of 43 long COVID trials included the face-to-face Pilates trial as its only Pilates trial, at low certainty. A 2023 review urged that "further research is needed" before exercise therapies such as Pilates are widely used in long COVID.
Across 14 trials (1,244 people), rehabilitation improved walking distance (moderate certainty) and breathlessness in the short term. A review of 50 trials (3,978 people, as corrected in 2026) found exercise training added 84.7 metres to a 6-minute walk, with most of the evidence low or very low certainty. A 2026 review of 12 studies (1,403 people) found no significant long-term effect. The REGAIN trial of online group rehabilitation in 585 adults after a hospital stay improved quality of life by a small amount; its video library included Pilates.
In a review of 8 exercise trials, "No studies in the current review directly assessed outcomes related to postexertional symptoms". So the trials tell us little about people with PEM.
In 31 people with PEM, single sessions of interval, moderate or strength exercise didn't worsen fatigue 2 days later more than in healthy people, but brought more muscle pain or concentration problems. In 25 people with PEM, one all-out test set off PEM in every one of them. Neither tested a training programme.
A 6-week online singing-based breathing programme (150 people) improved the mental health side of quality of life and breathlessness when running, but not the physical side. Home breathing-muscle training didn't change overall respiratory quality of life. The WHO rates breathing treatments in long COVID as very low certainty.
The WHO says oxygen drops on exertion and heart problems "should be ruled out and managed before consideration of physical exercise training". The NHS says to "be careful when exercising and stop if you have any symptoms".
Start with a short lying and seated routine, such as our long COVID gentle routine. Keep the same amount for at least a week, and add a little only if nothing got worse; at any sign of PEM, drop back and pace (our exercise for long COVID guide's editorial rule).
Source 4
Once that routine has been steady for at least a week, add a few Pilates floor moves at below their usual amounts (below), then seated chair Pilates. A gentle class may suit later (our suggestion).
In the one trial that compared them, face-to-face mat Pilates helped where recorded online classes didn't. In a class, tell the teacher about PEM and any dizziness (our suggestion).
Source 6
If you've recovered with no ongoing symptoms, ease back with shorter, easier sessions (our suggestion). In 145 students after mild COVID-19, 3 months of Pilates improved core endurance and balance more than a home programme. If symptoms carry on beyond 4 weeks, or come back when you're active, talk to a GP before you exercise again.
New or worsening breathlessness needs checking before any breathing exercises.
Slow, quiet breathing through your nose, a little longer out, and pursed-lip breathing when you're breathless help many people feel more in control. The evidence for breathing treatments in long COVID is very low certainty.
A respiratory physiotherapist can assess and treat it; retraining starts at rest, before any exercise.
Source 13
Our yoga for long COVID guide leaves out breath of fire and bellows breath and keeps holds short or out; do the same in Pilates.
With dizziness on standing, keep your moves lying or seated, change position slowly, and see a GP: it may be PoTS, which you may be more likely to have with long COVID. Our Pilates for POTS guide has a 20-minute floor class that never asks you to stand.
Source 8
Lie down and raise your legs until you feel better. If you can't lie down, sit, if possible with your head lowered between your knees, and drink some water.
If you feel faint, stop, lie down and raise your legs. Use the counter-manoeuvres if you can't lie down.
Cross one leg in front of the other while standing, then tense your leg muscles and clench your buttock and tummy muscles. You can also rock up and down on your toes, or clench your fists. Keep breathing while you hold the squeeze, sit or lie down as soon as you can, and practise when you're well so the moves come quickly (our suggestions).
If you faint while exercising, call 999 (911 in the US).
Source 38
The getting-up steps from our Pilates for hypermobility guide, as our Pilates for POTS guide uses them.
Slow breathing: a few minutes to start a rest, with no holds (our ME/CFS guide's editorial starting point; adapted from the move page's dose), small, quiet breaths through your nose, a little longer out. Lateral breathing: 3 to 5 easy breaths, optional (our editorial starting point; adapted from the move page's dose); stop if you feel light-headed. Pursed-lip breathing, for breathlessness: "To learn it, practise 5 to 10 breaths sitting down, once or twice a day, until it comes naturally" (from the move page's dose). Corpse pose as part of a planned rest, propped up or on your side if lying flat makes you breathless.
Only on a stable day, within your energy limit, spread through the day and judged over the next 2 to 3 days: 3 to 5 slow ankle circles each way, heel slides, shoulder rolls, knee folds or seated rotations, and 30 seconds of seated marching (our ME/CFS guide's editorial starting point, each adapted from the move page's dose); breath reach: 3 breaths, arms only as high as is comfortable (our editorial starting point). Choose 2 or 3, not all of them, and stop well before you feel tired.
 3D demoAnkle circlesBeginner · No equipment
 3D demoSupine heel slideBeginner · No equipment
 3D demoShoulder rollsBeginner · No equipment
 3D demoKnee foldBeginner · No equipment
 3D demoSeated marchBeginner · A bench or box
 3D demoThoracic rotationBeginner · No equipment
 3D demoBreath reachBeginner · No equipment
Our long COVID gentle routine's doses: bridge 5, lifting only a little; seated knee extension 5 each leg, no weight; seated calf raise 10; sit to stand 5, standing up slowly; wall push-up 5; slow calf raise 10, holding a support (standing only if you're not dizzy); legs up the wall 2 minutes, or legs on cushions, coming up slowly. Once that has been steady for at least a week: side kick 5 each side, clamshell 5 each side and chest lift 5, head down between lifts (our editorial starting point, below the usual amounts; the side kick and chest lift are adapted from their move pages' doses).
 3D demoGlute bridgeBeginner · No equipment
 3D demoSeated knee extension (chair)Beginner · A bench or box + Something with weight
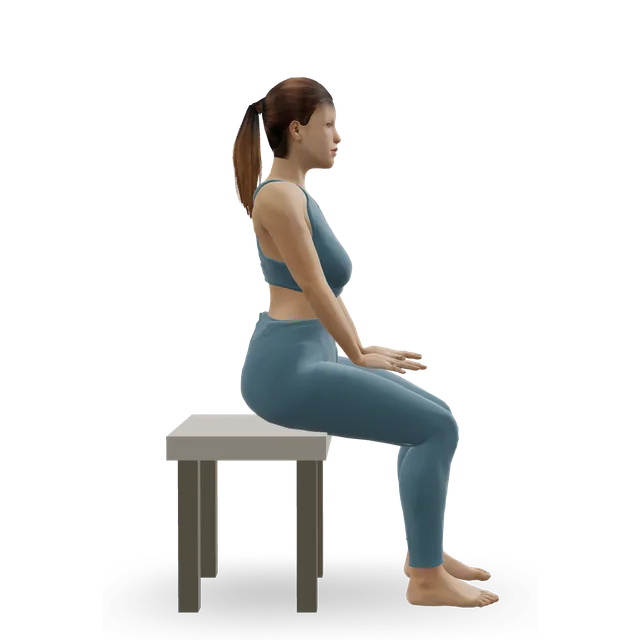 3D demoSeated bent-knee calf raise (soleus raise)Beginner · A bench or box
 3D demoSit to stand from a chairBeginner · A bench or box
 3D demoWall push-upBeginner · A wall
 3D demoSlow calf raiseBeginner · A wall
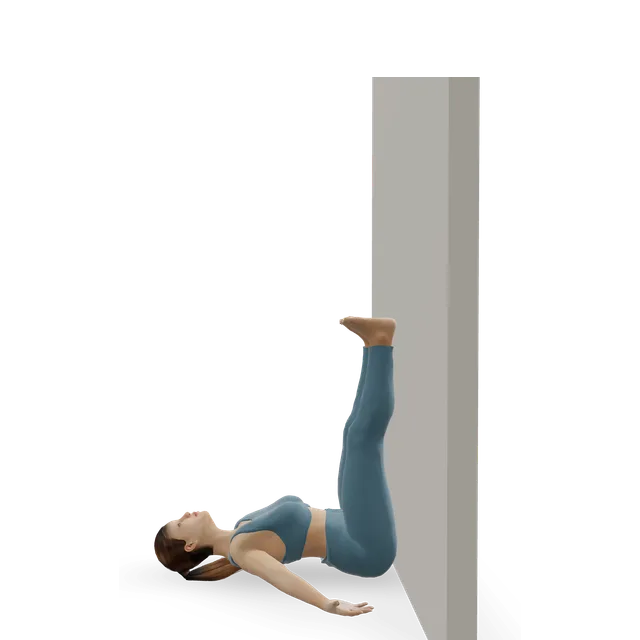 3D demoLegs up the wall (Viparita Karani)Beginner · A wall
 3D demoSide kick (Pilates side kick series)Beginner · No equipment
 3D demoClamshellBeginner · No equipment
 3D demoChest lift (Pilates curl-up)Beginner · No equipment
Including reformer and hot classes: NICE says not to offer "generalised physical activity or exercise programmes" in ME/CFS, and the WHO and World Physiotherapy advise against graded exercise and fixed activity plans with PEM. Without PEM, a gentle class may suit once the gentle routine has been steady (our suggestion).
Add-a-minute plans and 30-day challenges, including our 30-day wall Pilates challenge, work the way graded exercise does.
The NHS PoTS advice is not to get up too quickly after lying down. Use the getting-up steps above.
Source 8
They're high effort for the time they take, and easy to hold your breath in (our suggestion).
Heat can make PoTS worse, and no study has tested hot classes in long COVID. We'd avoid them, as our yoga for long COVID guide does.
Source 8
A follow-along class of fixed length is the kind of general programme NICE advises against in ME/CFS, and the WHO and World Physiotherapy advise against fixed increases. Our Pilates for chronic fatigue and yoga for long COVID guides made the same choice.
Our long COVID gentle routine already starts lying down, and the routines below can follow it, with conditions.
With PEM, only the slow breathing in the breathing routine, at the start of a rest, leaving out the box and 4-7-8 holds. Without PEM, or with your long COVID team's agreement, and after chest pain, breathlessness or palpitations have been checked: the gentle routine first; the floor Pilates class for PoTS if you have PoTS, with its own rule to stop increasing if a crash follows; and seated chair Pilates once the gentle routine has been steady for at least a week (our suggestion).
A 6-minute breathing routine: slow breathing, crocodile breathing, alternate nostril breathing, box breathing and 4-7-8 breathing.
6 minBeginner5 movesNo equipmentA 12-minute routine for long COVID that starts lying down and stays mostly seated: breathing, gentle leg and arm moves, and legs up to finish.
12 minBeginner13 movesA bench or box, Something with weightA 20-minute floor Pilates class for PoTS (POTS): breathing, leg strength and core work lying down and on your side, then legs up the wall, with no standing.
20 minBeginner14 movesOther / check instructions, A wallA 15-minute chair Pilates class done entirely sitting down, in a chair or wheelchair: breathing, spine moves, and leg and arm strength with water bottles.
15 minBeginner13 movesA bench or box, Something with weightThe 999, same-day, NHS 111, GP, step-back and mental health lines are from our exercise for long COVID guide, word for word; the palpitations line is from our yoga for long COVID guide, and the PEM and PoTS lines from our Pilates for chronic fatigue and POTS guides. This is general information, not a diagnosis. A&E means accident and emergency; in the US, call 911 for 999, and use your doctor's urgent line or urgent care for NHS 111.
Call 999 if you or someone else has any of these, and don't drive yourself to A&E:
If a pulse oximeter shows your oxygen falling when you move, or you get chest pain when you exert yourself, stop and get medical advice the same day. NICE asks for urgent referral for low oxygen on exercise, signs of severe lung disease and heart-type chest pain.
If symptoms come back or new ones appear during or in the days after activity, stop and seek advice. After a crash, cut back, rest, and don't return to your usual level until it has settled.
If your symptoms get worse during an activity or over the next 2 to 3 days, drop back and rest, and don't return to your usual level until the flare-up has settled.
Source 3
If exercise is followed by a crash a day or more later that's out of proportion to what you did, stop increasing and talk to your specialist: it may be PEM.
Source 8
NICE asks for urgent mental health assessment for severe symptoms or a risk of self-harm. If you're thinking about suicide or can't keep yourself safe, call 999 or go to A&E. For urgent help, call Samaritans free on 116 123, any time, or in England call 111 and select the mental health option. In the US, call or text 988.
Source 35
You feel any pain or become unwell, as the NHS advises for its Pilates videos, and especially for chest pain or pressure, unusual breathlessness, dizziness or fainting. If you have a health problem, an injury or any symptoms, get advice from a healthcare professional, such as a GP, before you start.
Source 42
The NHS advises getting advice from a healthcare professional first if you have a health problem, an injury or symptoms, or have recently had a heart attack or an operation.
Source 42
With PEM, NICE says not to push through symptoms (in ME/CFS), and World Physiotherapy says "Stop. Rest. Pace".
PEM can follow minimal physical, mental, emotional or social activity, and a class adds travel, talking, counting, light and noise to the moves.
Source 3
The WHO says fixed increases and graded exercise "should not be offered to people experiencing PESE", and NICE rules out fixed increases in ME/CFS.
PEM typically comes 12 to 48 hours later (NICE) or 12 to 72 hours later (WHO). Judge a session over 2 to 3 days.
"There's currently no cure for long COVID", the NHS says. The Pilates trials are small, didn't check for PEM, and one found that online Pilates did nothing.
New or worsening breathlessness needs checking first. Breathing programmes helped some outcomes in trials, on low or very low certainty evidence.
Lost fitness is part of the picture for some people, but in people with PEM a single all-out test set off PEM with muscle damage, and the guidance for PEM is pacing. One US heart association statement takes the deconditioning view; this page follows NICE.
It might help some people, but only after you've checked for post-exertional malaise (PEM). In two small trials, people with long COVID who did Pilates had less fatigue and walked further, but neither checked for PEM, which many people with long COVID have. With PEM, pacing comes first, not a Pilates class.
Yes, if it's more than you can manage, especially with PEM, which can follow even small physical, mental or social effort 12 to 72 hours later. Judge any session over the next 2 to 3 days, and drop back if your symptoms get worse.
Our long COVID exercise guide has a 5-question check, adapted from a questionnaire tested in ME/CFS. If any of its signs happen about half the time or more and bother you moderately or more, treat it as PEM and talk to your GP or long COVID team.
NICE's long COVID guideline asks for a personalised rehabilitation plan after checks, and lists how well exercise works as a research question. Where PEM is present, we follow NICE's ME/CFS guideline: no graded exercise, no fixed increases, and pacing within your energy limits.
Without PEM, and once chest pain, breathlessness or palpitations have been checked, a gentle class may suit after you've done a short home routine steadily for a while. With PEM, a full class is too much for most people, because the journey, the talking and the noise use energy too.
Pilates on equipment has only been tested after severe COVID-19, in a small study that hasn't been peer reviewed. Reformer classes are usually full-length general classes, so the same rules apply: without PEM, start very gently; with PEM, don't.
Slow breathing and small moves lying down or seated, such as heel slides, knee folds, ankle circles and seated marching, a few at a time and spread through the day. Leave out planks, roll-ups, teasers and quick changes between the floor and standing.
Two small trials reported less fatigue after 8 to 12 weeks of Pilates, but neither checked for PEM, and online Pilates made no difference in the trial that tested it. If your fatigue gets worse a day or two after activity, that may be PEM, and pacing comes first.
Get new or worsening breathlessness checked first. Slow nose breathing and pursed-lip breathing help many people feel more in control, and a physiotherapist can treat a breathing pattern disorder; the evidence for breathing treatments in long COVID is weak.
Do your moves lying or seated, change position slowly, and see your GP: it may be PoTS, which you may be more likely to have with long COVID. Our Pilates for POTS guide has a class that never asks you to stand.
If you've recovered with no ongoing symptoms, ease back in with shorter, easier sessions. If symptoms carry on beyond 4 weeks, or come back when you're active, talk to a GP before you start exercising again, as the NHS advises for long COVID.
In the one trial that compared them, face-to-face mat Pilates reduced fatigue and improved walking, while recorded online classes didn't. That's one small trial; a live, supervised session lets a teacher adjust things for you.
Exercise education, not a personal prescription, and clinical review of these guides is pending. If you are pregnant, have a health condition or have had recent surgery, check with a doctor, midwife or physiotherapist before starting, and stop for sharp or increasing pain. Health disclaimer.






