Pain guide · Foot pain

Foot pain from jump rope: the ball of the foot, arch and heel, stress fractures, floors and shoes

Foot pain from jump rope usually comes from doing too much too soon on a hard floor. Skipping is a quick bounce on the front of your foot, about twice a second, and in lab studies the ball of the foot and the big toe took the highest pressures with each landing; by our own arithmetic, ten minutes means well over a thousand landings. Where it hurts is the best clue: an ache under the ball of the foot is usually metatarsalgia, burning between the toes Morton's neuroma, a pain under the big toe joint sesamoiditis, a sharp heel on the first steps plantar heel pain, and one spot on a bone that hurts with every landing and later at rest a possible stress fracture, which needs checking before you skip again. Jumping lower, shorter rounds with rest days, a forgiving floor and cushioned shoes usually help. Jump rope isn't bad for your feet when it is built up gradually. No study has counted foot pain from jump rope, so this guide says where each piece of advice comes from.

This guide starts with the signs that need help, from a 999 call or accident and emergency (A&E) for a foot that is out of shape, numb or cold after an injury, to a same-day check through the National Health Service's 111 line (NHS 111) for a snap or kick at the back of the ankle, a foot you can't walk on, a hot, swollen joint or any new foot problem with diabetes, and a general practitioner (GP) for one sore spot on a bone. It then maps the causes by where it hurts, explains what the studies show about landings, floors, shoes and how many jumps, and when a scan helps, shows how to change your skipping today, and gives a three-stage plan with a 3D demo of every move, from calf raises back to the rope.

When to get help first

Exercise is for pain that has been checked or is clearly mild and settling.

Get urgent medical help if

  • Call 999 or go to A&E: after an injury, you heard a crack, the foot or ankle has changed shape or points at an odd angle, a bone is sticking out, there is a bad cut over it, you're in severe pain, or the toes look blue or white, feel numb or are cold to touch. These can mean a broken bone. Don't drive yourself.
  • Same day (NHS 111 or an urgent treatment centre): after an injury, you can't put weight on it or walk more than a few steps, the pain is very bad or getting worse, there is a lot of swelling or bruising or it is getting worse, it feels very stiff, or it's not feeling any better after treating it yourself. Get the same help if you also have a very high temperature, or feel hot, cold or shivery: this could be an infection. If you think it's broken, don't treat it yourself.
  • Same day: a sudden snap or pop at the back of the heel or calf, or a feeling of being kicked there, then walking flat-footed and being unable to push off, stand on tiptoe or climb stairs. It could be an Achilles tendon rupture or a broken heel bone. Go to A&E or a minor injuries unit, or contact NHS 111.
  • Same day (urgent GP appointment or NHS 111): sudden, severe pain in one joint, with swelling, a change in skin colour or difficulty moving it, especially if you feel unwell, hot, cold or shivery or have a high temperature (although not everyone has one). It could be an infection in the joint, gout or calcium crystals (pseudogout), and only a sample of fluid from the joint can tell them apart.
  • Call 999 or go to A&E: you have diabetes and a foot ulcer with a fever or signs of sepsis, an ulcer with poor circulation, a possible deep infection of the soft tissues or bone in the foot (with or without an ulcer), or gangrene. NICE asks for these to go straight to hospital.
  • Same day: you have diabetes and a new foot problem, such as an ulcer or wound, signs of infection, or a hot, swollen foot with a change in colour, even if it doesn't hurt. Contact your diabetes foot team or GP: NICE asks for these to reach a specialist foot service within 1 working day, and a suspected Charcot foot is kept off weight until it has been checked.
  • If you have diabetes, see your local foot team urgently, within 24 hours, for a change in the colour or shape of your foot (especially a red, hot, swollen toe, ankle or foot), part of your foot feeling much colder or hotter than usual, new blisters, cuts or wounds (especially ones you can see but don't feel), a cut or wound that smells bad or is leaking fluid or pus, or new or unexplained pain in your foot. Meanwhile sit or lie down, take the weight off it and raise it.
  • Call 999 or go to A&E: a foot or leg that is suddenly cold, pale, numb, weak or very painful without an injury. A sudden loss of blood supply is a vascular emergency.
  • Same day (urgent GP appointment or NHS 111): throbbing pain in one leg (rarely both), usually the calf or thigh; swelling in one leg (rarely both); red, blue or darkened skin around the painful area, which may be harder to see on brown or black skin; or swollen veins. It could be a blood clot (DVT). Watch for it after an ankle injury or time in a cast or boot.
  • Call 999 or go to A&E if breathing suddenly becomes difficult, if pain in your chest or upper back comes on suddenly with breathlessness or a very fast heartbeat, or if someone passes out. Do not drive yourself. It can be a blood clot that has reached the lungs.
  • Call 999 or go to A&E: sudden, severe pain in a muscle, which may be worse when you stretch it, with swelling, numbness, weakness or pins and needles, or tightness or difficulty moving the leg. This can be acute compartment syndrome, which needs surgery as soon as possible. It usually follows an injury or a bandage or cast that is too tight, but rarely it can follow very hard exercise. Do not drive yourself to A&E.
  • Same day (call NHS 111, or go to A&E if you feel very unwell): after a big or unusual session, such as a first spin class, a workout of 100 back squats, or intervals of wall sits, squats, lunges and jumps, a challenge or a new class, muscle pain, swelling or weakness far worse than the session explains, and dark pee (red, brown, tea or cola coloured), sometimes starting hours or days later. Dark pee isn't always there, so muscles far sorer, more swollen or weaker than the session explains still need the same-day check. It can be rhabdomyolysis, a breakdown of muscle that can harm the kidneys.
  • Call 999: shoulder or arm pain with chest pain that feels tight or squeezing, or chest pain that spreads to your arms, neck or jaw, especially with shortness of breath, sweating or feeling sick. It could be a heart attack.
  • Someone who faints while exercising, or who has fainted and can't be woken within a minute, has chest pain or a pounding, fluttering or irregular heartbeat, or hasn't fully recovered.

See a doctor or physiotherapist if

  • Pain in one spot on the shin or a foot bone that you can point to with a fingertip, worse with impact and later present at rest or at night: a possible stress fracture. Stop running and jumping until it has been checked.
  • One spot on a foot bone that hurts with every step and later at night: a possible stress fracture.
  • Pain at one spot on a foot bone that makes you limp, or that hurts when you walk the next day: stop jumping and see a GP, podiatrist or physiotherapist within a few days. It could be a stress fracture, which can become a complete break if you keep loading it (our suggestion).
  • Pain in the middle of the foot that is hard to pinpoint, on the outer edge of the midfoot, or on the front of the shin bone in a running or jumping athlete. These sites heal less well and need prompt assessment, often with a scan.
  • A stress fracture from ordinary activity, more than one stress fracture, periods that have stopped or become irregular, or worries that you're eating too little for your training: see a GP about bone health and energy intake.
  • Pain in one spot under the big toe joint that hurts with every step and later at rest or at night, especially after a rise in training: a possible stress fracture of a sesamoid, which heals slowly. Take the load off it until it has been checked.
  • Pain that started when the big toe was forced backwards, or you can't push off: a possible fracture or a sprain of the joint, which the turf toe guide covers.
  • You can't put weight through the ball of the foot, or the pain is severe without any injury: a podiatry consensus advises referral for further assessment.
  • Tightness in the shin or calf, with tingling on the top of the foot or a foot that slaps down, that comes on at the same point in every run and eases within minutes of stopping: see a GP or sports physiotherapist. It can be exertional compartment syndrome.
  • Pain that isn't better after 2 weeks of looking after it yourself, is getting worse, keeps coming back, or stops you doing normal things.
  • Tingling or loss of feeling in the foot, or a foot that feels weak.
  • Any foot pain if you have diabetes: foot problems can be more serious.
  • A child's heel or foot pain that isn't clearly linked to activity, or that comes with swelling or redness. With a high temperature, or if your child seems unwell, get help the same day: an urgent GP appointment or NHS 111.

Where does it hurt?

Location narrows the likely causes; it does not diagnose.

An ache under the ball of the foot, across the joints at the base of the toes, during and after rounds

Usually metatarsalgia. Fewer rounds, cushioned shoes and a soft forefoot insole or pad usually help.

Read: Ball of foot pain →
Burning, shooting or a pebble feeling between the 3rd and 4th toes, sometimes with tingling

Often Morton's neuroma. Wide shoes, a metatarsal pad and less jumping usually help.

Read: Morton's neuroma →
Under the joint at the base of the second toe, the toe drifting or lifting

Possibly a plantar plate injury. Taping and offloading pads are the usual first steps.

Read: Plantar plate tear →
Under the big toe joint, worse pushing off or on tiptoe

Often sesamoiditis. One spot there that hurts with every landing can be a sesamoid stress fracture: take the load off it until it's checked.

Read: Sesamoiditis →
One spot on a long foot bone you can point to with a fingertip, after more jumping than usual, later aching at rest or at night

A possible stress fracture, most often of the second or third metatarsal: stop jumping and get it checked.

Read: Stress fracture →
A vague ache on top of the inner midfoot, hard to pin down, worse with sprints, push-off and jumps

A possible navicular stress fracture, which heals less well and needs prompt assessment, often with a scan.

Read: Stress fracture →
The bump halfway along the outer edge of the foot, sore with push-off and turns

Possibly a stress fracture at the base of the fifth metatarsal, a site that heals less well: get it checked.

Read: Broken foot (metatarsal fracture) →
Along the tendons on top of the foot, worse with tight laces or new shoes

Usually irritated tendons on top of the foot. Loosen the laces over the sore spot.

Read: Pain on top of the foot →
Under the heel, worst on the first steps after rest

Usually plantar heel pain (plantar fasciitis). Stretching, taping and cushioned heels help most people.

Read: Plantar fasciitis (plantar heel pain) →
Along the arch, after long sessions

Often the plantar fascia or a tired arch.

Read: Arch pain →
The back of the heel where the tendon joins the bone, stiff in the morning after a big session

Often Achilles tendon pain. A snap or a kick at the back of the ankle is different: see the warning signs.

Read: Achilles tendinopathy →
The inner edge of the shin, along the bone, building over sessions

Usually shin splints, more likely on hard floors.

Read: Shin splints →
The calves, sore for a day or two after your first sessions

Usually muscle soreness: the calves do most of the work in skipping.

Read: Calf pain →
A sudden, hot, red, swollen big toe joint without an injury

Often gout, which needs help the same day, as the warning signs say.

Read: Big toe pain →
The knees when you skip

Our jumping knee guide covers landings, skipping and a plan back.

Read: Knee pain when jumping →

Understand it

What jump rope asks of the foot, and what no study has countedEmerging evidence

Skipping is a low, quick bounce on the balls of your feet, and the calves and Achilles tendons do most of the spring. In 10 men skipping in shoes at 2.2 jumps a second, the heel barely touched down on two feet, and the highest pressures sat under the middle of the forefoot. In 26 competitive skippers doing the fast speed step, the forefoot took the greatest load, with the big toe and the joints at the base of the first three toes under the most stress. In 16 teenage boys, the big toe joints bent back more than 50 degrees, which the authors suggest could be an injury risk.

Landing forces vary between studies. Through a force plate, peaks were about 3.3 to 3.6 times body weight on one leg and 4.3 to 4.6 on two in shod men (two studies of 10), and about 2.8 to 2.9 times body weight per step in the alternate-foot step in experienced skippers; in barefoot Muay Thai athletes the reported forces were higher still, by our arithmetic from their body weights. Studies used different methods, and one study's figures can't be read as body weights, so these are rough guides, not exact numbers. Double-unders and the speed step made the ankle absorb up to about twice the power of running in 16 young competitive skippers.

No study has counted foot pain or injury from rope jumping. In a 1986 trial of 26 inactive adults, the group skipping 10 minutes a day, 5 days a week had more injuries and drop-outs than joggers, without counts, and later rope training trials report no injuries. So the map on this page is built from what each condition is known to do.

Sources 1, 2, 3, 4, 5, 6, 7, 8, 9

How many landings, and why volume is the usual storyEmerging evidence

People hop at about 2.2 times a second by preference, so by our own arithmetic 5 one-minute rounds are about 660 landings and 10 minutes over 1,000. Bone stress injuries follow an error in workload, when the number and size of the loads outstrip the bone's ability to cope. In 2 men with strain gauges on the second metatarsal, jumps strained the bone more than barefoot walking; in elite infantry recruits, 91% of stress fractures in the third training phase were metatarsal; and a review of 32 studies found high exercise intensity, training that doesn't adapt and poor equipment raised the risk of metatarsal stress fractures.

Health New Zealand lists running and jumping without enough rest, a sudden increase in activity, and worn-out shoes or hard surfaces among the causes of stress fractures, and the AAOS (American Academy of Orthopaedic Surgeons) says doing too much, too soon is a common cause. In our reading, a new rope habit, a daily challenge or a jump from 5 to 20 minutes is the commonest story, not the rope itself.

Sources 10, 11, 12, 13, 14, 15, 16

Where it hurts, and what it usually is

No study counts the causes of foot pain from skipping, so these come from the conditions' own evidence and the NHS.

  • The ball of the foot: metatarsalgia, which the NHS links with exercise such as running and with tight shoes; Morton's neuroma (burning or a pebble feeling between the 3rd and 4th toes); or a plantar plate injury under the base of the second toe.
  • Under the big toe joint: sesamoiditis, which the AAOS says is common in ballet dancers and runners, or a sesamoid stress fracture.
  • One spot on a long foot bone: a possible stress fracture, most often of the second or third metatarsal, which take the greatest force as you push off.
  • The heel and arch: plantar heel pain; the NHS names exercising on hard surfaces among its causes.
  • The top of the foot: the NHS says pain there is often caused by exercise, especially running, kicking or jumping, and tight shoes.
  • The shins: shin splints, which the NHS links with running or jumping on hard surfaces.

Sources 17, 18, 19, 20, 16, 21, 22, 23, 24

Who gets itEmerging evidence

In our reading: people new to skipping or coming back after a break, especially those who start with daily sessions; boxers, CrossFit athletes and class-goers adding double-unders or speed steps; people skipping on concrete or in worn, thin or tight shoes; and anyone not eating enough for their training, since low energy availability is a major risk factor for bone stress injuries. Bone stress injuries are 1.8 to 2.3 times as common in female athletes as in male athletes. People with diabetes and numb feet need to check their feet after sessions, because pain won't warn them.

Serious causes are uncommon: a stress fracture at a high-risk site, a broken bone after a fall or a tangled rope, an Achilles rupture, a hot joint, a clot, and, with diabetes, a foot ulcer or a hot, swollen foot. The warning signs pick them out.

Sources 8, 7, 25, 15

When a scan or test mattersStrong evidence

Not at first for a gradual ache under the ball of the foot, the heel or the arch: the NHS starts with rest, ice, soft insoles or pads and a GP if it hasn't improved after 2 weeks. For one spot on a bone, an X-ray comes first, but stress fractures can be hard to see early: in 64 stress fractures at the base of the second metatarsal in dancers, the first X-rays were negative in 42. The AAOS says a navicular stress fracture may need a computed tomography (CT) or MRI scan, and a sesamoid fracture an MRI or bone scan. For Morton's neuroma, a click that you notice makes it more likely, and a negative tenderness test, pressing between the toes, makes it unlikely.

Sources 17, 22, 26, 16, 27

How it usually goesEmerging evidence

No study follows foot pain from jump rope. The NHS says pain in the top of the foot usually gets better in a few weeks and suggests a GP if ball-of-foot pain hasn't improved after 2 weeks. A stress fracture usually takes 6 to 8 weeks to heal, and as long as you can feel pain, the bone is still fragile. Over 90% of athletes return to sport after a bone stress injury, but the navicular took a pooled 127 days, and navicular fractures were found after a mean of almost 10 months of symptoms.

Plantar heel pain is often slow: in 174 hospital patients, 80.5% were still affected after a year and 50% after 5 years. Sesamoiditis outcomes are mixed: in one series, 45.4% returned to pain-free sport. No one can promise a date.

Sources 21, 17, 15, 28, 29, 30, 31

What helps, and how strong the evidence is

Lower, fewer, softer: changes from health-service advice and lab studies (untested for pain)Emerging evidence

No trial has tested a change to jump rope for foot pain. Daily rope from scratch brought more injuries and drop-outs than jogging in one small trial, so short rounds 2 or 3 days a week come first. Faster rope speeds shortened contact and shrank ankle movement (from about 53 to 21 degrees), and double-unders loaded the ankle more than running, so plain two-foot bounces come before speed work. Health New Zealand names hard surfaces among the causes of stress fractures, and the NHS names exercise on hard surfaces for plantar fasciitis and shin splints.

Sources 8, 7, 32, 15, 33, 24

Floors and shoes help less clearly than people thinkMixed evidence

In experienced skippers, shoes slowed how fast each landing built up compared with bare feet (about 44 against 62 times body weight per second) without lowering the peak. On softer surfaces people stiffen their legs, keeping the bounce much the same. In aerobic dance (411 people), injury rates depended on how the programme was run, not on the brand of shoe or the type of floor. Cushioned shoes raised impact in single-leg landings compared with minimal shoes or bare feet in 14 people, while bare feet raised the peak in other landings. So a forgiving floor and comfortable shoes are sensible, and how much you skip matters more.

Sources 6, 34, 35, 36, 37

Stress fractures: no impact until it's pain-freeEmerging evidence

For low-risk metatarsal stress fractures, an expert review advises load that causes no symptoms during, after or the day after, and a return to running once daily activities have been pain-free for 5 days in a row, with jumping later. Health New Zealand says stop the activity that caused it, and you may need a boot or crutches. The AAOS says a fifth metatarsal base fracture usually means at least 6 weeks off weight in a cast or boot, and sport not before about 12 weeks. Navicular fractures did better with surgery than without in pooled studies (97.9% against 78.1% success). These are decisions for your clinician; the guide's job is to get you seen early.

Sources 38, 15, 16, 29

The ball of the foot and the toesEmerging evidence

The NHS suggests rest, ice, wide shoes with a low heel and soft sole, and soft insoles or pads. A forefoot cushioning insole lowered forefoot pressure in 23 runners, but a metatarsal pad didn't; in 13 people with metatarsalgia, the pads that lowered pressure most eased pain most. For a plantar plate injury, care starts with taping and offloading pads. For Morton's neuroma, the NHS suggests wide shoes, soft pads and less running and jumping, and a steroid injection improved foot health scores for at least 3 months in a 131-person trial. For sesamoiditis, the AAOS suggests soft-soled shoes and a cushioning pad; pain improved in about two-thirds of pooled cases, all small series.

Sources 17, 39, 40, 41, 18, 42, 20, 31

Heel pain: stretching, taping and education firstStrong evidence

A best practice guide built from 51 trials (4,351 people) puts taping, stretching and education at the core of care for plantar heel pain; stretching and taping both eased first-step pain. In 48 people, high-load heel raises with a towel under the toes, every second day, gave a foot function score 29 points better than stretching at 3 months, with no difference at 1, 6 or 12 months. The NHS adds cushioned heels and arch support and not walking barefoot on hard surfaces.

Sources 43, 44, 33

Rope training is good for you, built up graduallyEmerging evidence

Across 21 studies, mostly of young people, rope training improved fitness, strength and sprinting a little, with no clear effect on bone mass; in 37 teenage girls, heel bone stiffness rose more over 4 months with 10 minutes of rope jumping than with none. Hops can load the Achilles tendon to several times body weight, up to 7.3 in a forward one-leg hop in 8 adults, which is why the calves need building up too.

Sources 9, 45, 46

How much pain is OK while you exercise?

Up to about 5 out of 10, settled within an hour, no worse the next morning; one sore spot on a bone should be pain-freeEmerging evidence

This guide uses the foot hub's rule, as our other foot guides do. Some discomfort during exercise is fine. Aim for pain you would call mild to moderate, no more than about 5 out of 10, that settles within an hour, with no more swelling or stiffness the next morning. If it's worse the next day, do a little less (a smaller range, fewer reps, a lighter band), not nothing.

The exceptions: pain in one spot on a bone should be pain-free, because it could be a stress fracture; burning, tingling or numbness means stop that movement; and if your feet are numb, pain won't warn you, so check your skin after exercise.

Our running foot guide adds that you should stop a run if a pain is sharp, makes you limp or change how you run, or builds as you go; the same goes for a round of skipping.

If pain climbs day after day, or you notice a warning sign, stop and get it checked. The 5 out of 10 figure is an editorial starting point that matches this site's other pain guides, not a tested rule.

For a possible stress fracture, an expert review aims for no symptoms during, after or the day after loading; continued loading under a pain-monitoring rule did no harm in Achilles tendon pain, and in 7 trials of long-lasting pain, exercise that allowed some pain did no worse than pain-free exercise.

For jump rope (our suggestion, built on the same rule): judge each round by how your feet feel during it and the next morning. Use the floor, the shoes, the height, the round length and the weekly minutes where your foot stays at 5 out of 10 or less, settles within an hour and is no stiffer or more swollen the next morning; with heel pain, your first steps the next morning should be no worse than usual. Calf soreness that fades within a day or two is the calves working. One spot on a bone that hurts, pain that makes you limp, burning or tingling in the toes, a snap at the back of the ankle, or a hot, swollen joint isn't a pain-rule question: see the warning signs.

Sources 15, 38, 47, 48

The exercise plan: 3 stages

Start at the first stage. Each move opens a full guide with a 3D demo.

Stage 1

Off the rope: settle the foot, keep fit, start loading

About weeks 0 to 2, longer with a suspected stress fracture, which follows its own guide: settle the pain with low-impact cardio, keep the calves and foot muscles working within the pain rule, and start heel loading if the heel is the problem. With a diagnosed condition (a stress fracture, Morton's neuroma, a plantar plate tear, sesamoiditis, plantar fasciitis, Achilles tendon pain), that guide's plan comes first.

Recumbent exercise bike demonstrated on the 3D figure3D demoRecumbent exercise bikeBeginner · Cardio machine

10 to 20 minutes at a moderate effort to start, building towards 30 (our editorial starting point). · The move page's dose. Only if it's pain-free at any sore bone, as our stress fracture guide says; swimming counts the same

Harder: Stationary cycling

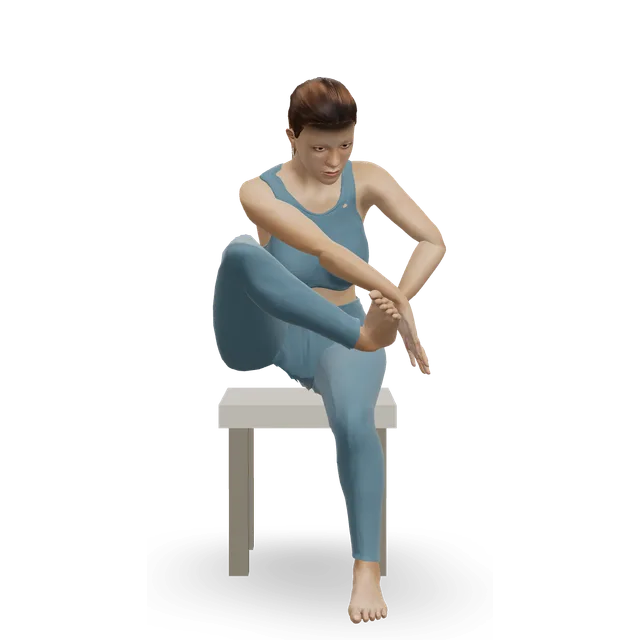
Plantar fascia stretch (seated) demonstrated on the 3D figure3D demoPlantar fascia stretch (seated)Beginner · A bench or box

3 to 5 holds of 10 to 30 seconds, 2 to 3 times a day, starting before your first steps in the morning. · The move page's dose; the hold length is the range used in trials. For heel or arch pain

Harder: Toes-tucked kneeling (toe squat)

Seated bent-knee calf raise (soleus raise) demonstrated on the 3D figure3D demoSeated bent-knee calf raise (soleus raise)Beginner · A bench or box

3 sets of 15 · As in our running foot guide (editorial)

Harder: Slow calf raise

Towel toe curl demonstrated on the 3D figure3D demoTowel toe curlBeginner · Other / check instructions + A bench or box

3 sets of 20 · As in our plantar fasciitis and running foot guides (editorial)

Easier: Big toe press (seated toe-flexor hold) · Harder: Short foot + toe splay

Heel raise with a towel under the toes demonstrated on the 3D figure3D demoHeel raise with a towel under the toesIntermediate · A step + Other / check instructions

Every second day, as in the trial. Start both feet, then one, at a load you can lift about 12 times for 3 sets, and progress over several weeks to heavier loads you can lift about 8 times, adding a backpack or dumbbell, as in the pre-set heavy-slow program. · The move page's dose, from the heel pain trial. For heel pain, once walking is comfortable

Easier: Slow calf raise · Harder: Standing dumbbell calf raise

Move on when: Walking is comfortable, first-step pain is easing, and no spot on a bone hurts to press, as our running foot guide asks (editorial).

Follow along: a timer, a cue and the next move, one step at a time.
Stage 2

Calf and foot strength, then gentle impact

About weeks 2 to 4, 3 or 4 sessions a week: calves and feet strong enough for hundreds of landings, then a little impact without a rope.

Slow calf raise demonstrated on the 3D figure3D demoSlow calf raiseBeginner · A wall

3 sets of 15, both feet, then one · As in our running foot guide (editorial). With ball-of-foot pain, stop short of full tiptoe, as the move page says

Easier: Seated bent-knee calf raise (soleus raise) · Harder: Standing dumbbell calf raise

Single-leg calf raise from a step demonstrated on the 3D figure3D demoSingle-leg calf raise from a stepIntermediate · A step + A wall

Build towards 20 slow reps each leg · As in our stress fracture guide (editorial)

Easier: Slow calf raise · Harder: Single-leg pogo hops

Tibialis raise demonstrated on the 3D figure3D demoTibialis raiseBeginner · No equipment

3 sets of 15 · As in our running foot guide (editorial)

Harder: Single-leg tibialis raise

Single-leg stand demonstrated on the 3D figure3D demoSingle-leg standBeginner · A wall

3 holds of 30 s each side · As in our running foot guide (editorial)

Easier: Tandem stance and heel-to-toe walk · Harder: Single-leg reach matrix

Step jack (low-impact jumping jack) demonstrated on the 3D figure3D demoStep jack (low-impact jumping jack)Beginner · No equipment

30 to 45 seconds within a circuit, 2 to 3 rounds: an editorial starting point. · The move page's dose; no trial has tested this move on its own. Cardio with no jumping

Easier: Seated march · Harder: Jumping jack

Ankle bounces (mini pogo) demonstrated on the 3D figure3D demoAnkle bounces (mini pogo)Beginner · No equipment

2 to 3 sets of 20, every other day · As in our running foot guide (editorial). Only once any sore bone is pain-free

Harder: Pogo hops

Move on when: 20 slow single-leg calf raises each side, a week of ankle bounces and your daily activities pass the pain rule with no sore spot on a bone; after a stress fracture, at least 5 days in a row pain-free in daily life first, as the expert review advises (editorial).

Follow along: a timer, a cue and the next move, one step at a time.
Stage 3

Back to the rope

From about week 4, later after a stress fracture, 2 or 3 sessions a week with a day off between: the rope back at a low dose, then your usual sessions, one change at a time by the written steps below. No study has tested a return to jump rope after foot pain, so the order is editorial, following the site's jump rope guide and its springy starter workout.

Pogo hops demonstrated on the 3D figure3D demoPogo hopsIntermediate · No equipment

3 sets of 20, once ankle bounces are easy · As in our running foot guide (editorial)

Easier: Ankle bounces (mini pogo) · Harder: Single-leg pogo hops

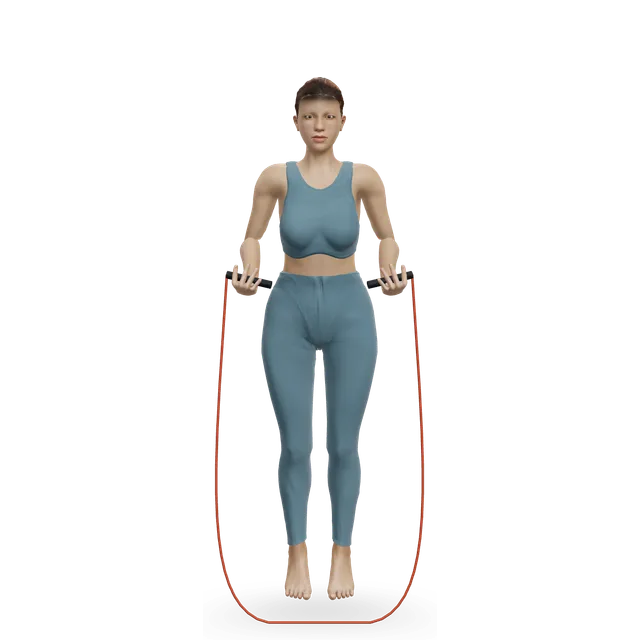
Jump rope (basic bounce) demonstrated on the 3D figure3D demoJump rope (basic bounce)Intermediate · A jump rope

5 rounds of 30 to 60 seconds with equal rest (our editorial starting point), adding no more than a few minutes in all each week. · The move page's dose. Two-foot bounces, about a centimetre high, on a forgiving floor

Easier: Ankle bounces (mini pogo) · Harder: Double-unders (jump rope)

Single-leg calf raise from a step demonstrated on the 3D figure3D demoSingle-leg calf raise from a stepIntermediate · A step + A wall

3 sets of 15 to 20 each leg, twice a week · As in our running foot guide (editorial): keep the calves strong while the rope comes back

Easier: Slow calf raise · Harder: Single-leg pogo hops

Double-unders (jump rope) demonstrated on the 3D figure3D demoDouble-unders (jump rope)Advanced · A jump rope

5 to 10 minutes of short practice sets, ending each before your form slips (our editorial starting point). Once they are consistent, 5 rounds of 20 to 30 with full rest. · The move page's dose. Last, only if you used them before; its caution says leave them out entirely during any calf or tendon flare

Easier: Jump rope (basic bounce)

Move on when: Your usual rope sessions pass the pain rule for 2 weeks: then the alternate-foot step, longer rounds, speed work and double-unders, one at a time, adding no more than a few minutes a week, as the site's jump rope guide says. Keep calf raises twice a week. If a session flares it, go back a stage for a few days, not to nothing (editorial).

Follow along: a timer, a cue and the next move, one step at a time.

What to change for now

Your jump rope for now (written steps)

Our 3D figure can't show the floor, your shoes, your jump height or how many rounds you do. These steps come from the site's jump rope guide and move pages, lab studies of rope jumping, health-service pages and expert reviews; no trial has tested a change to jump rope for foot pain, and each step names its source or says it is our suggestion.

  • 1. Height: about a centimetre, landing softly on the balls of your feet with your knees slightly bent; single bounces can let the heels touch lightly (our jump rope guide).
  • 2. Volume: 5 rounds of 30 to 60 seconds with equal rest, 2 or 3 days a week, adding no more than a few minutes in all each week (our jump rope guide and move page); daily rope from scratch brought more injuries and drop-outs in a small trial.
  • 3. Floor: a wooden or sprung floor or a rubber mat, not concrete (Health New Zealand and the NHS name hard surfaces; our jump rope guide).
  • 4. Shoes: cushioned trainers that fit, with room for your toes, not worn-out or thin-soled shoes (the AAOS and Health New Zealand; our jump rope guide). Shoes slowed how fast each landing built up in a lab study.
  • 5. Laces: loosen them over a sore top of the foot, or skip an eyelet there (our running foot guide's suggestion).
  • 6. Style: two-foot bounces first; the alternate-foot step, speed steps and double-unders later (our reading of the rope lab studies).
  • 7. A soft forefoot insole or pad with ball-of-foot pain (the NHS; a forefoot cushion lowered pressure in runners), and a cushioning pad with sesamoid pain (the AAOS).
  • 8. End a round when your landings get loud or your timing goes, as our jump rope guide says.

Sources 8, 15, 33, 24, 16, 6, 7, 17, 39, 20

Keep fit, and everyday life (written steps)

Our suggestions unless a source is named.

  • 1. The NHS's first steps for foot pain: rest and raise the foot when you can, an ice pack in a towel for up to 20 minutes every 2 to 3 hours, wide shoes with a low heel and soft sole, soft insoles or pads, and painkillers such as paracetamol or ibuprofen gel.
  • 2. Cardio without the impact: the NHS suggests swimming for plantar fasciitis and yoga or swimming while shin splints heal, and Health New Zealand suggests swimming and aqua jogging while a stress fracture heals; cycling, rowing, the elliptical and our low-impact cardio workout work too.
  • 3. Standing at work: cushioned shoes and short breaks; the NHS heel pain page says don't walk or stand for long periods, especially barefoot.
  • 4. Boxing, CrossFit and classes: step jacks, a fast march, standing punches or the bike for the conditioning rounds until stage 3 passes, and double-unders last.
  • 5. Running and court sports: once rope sessions pass the rule; after a stress fracture, our stress fracture guide's walk-jog plan.
  • 6. Diabetes with numb feet: check your feet after every session, and prefer low-impact options, as our jump rope guide suggests.

Sources 17, 21, 22, 33, 24, 15

Positions to swap, and why

Habit or positionWhy it mattersInstead
Skipping on through one sore spot on a boneIt could be a stress fracture, which can become a complete break if you keep loading it.Stop jumping and get it checked; cycle or swim meanwhile.Try: Recumbent exercise bike
Daily sessions from day oneDaily rope from scratch brought more injuries and drop-outs than jogging in a small trial.2 or 3 sessions a week with a day off between.
Skipping on concreteHealth New Zealand and the NHS name hard surfaces among the causes of stress fractures, plantar fasciitis and shin splints.A wooden floor, a sprung floor or a mat.
High, loopy jumpsHigher jumps and faster turns load the ankle more (our reading of the lab studies).About a centimetre off the floor.
Double-unders and speed steps while it's soreThe ankle absorbed up to about twice the power of running in a lab study.Two-foot bounces, later.Try: Jump rope (basic bounce)
Thin, worn or tight shoesWorn shoes are a stress fracture risk, and tight shoes are named for ball-of-foot and Morton's pain.Cushioned shoes that fit.
Barefoot skipping on hard floors with heel painThe NHS says try not to walk barefoot on hard surfaces with plantar fasciitis.Cushioned shoes.
A big jump in minutes, or a new challengeA sudden increase in activity is the commonest cause of stress fractures, the AAOS says.Add no more than a few minutes a week.
Hopping and pogo hops with a possible stress fractureImpact should be pain-free first, as the expert review advises.Calf raises and the bike.Try: Slow calf raise
Pushing on through burning or tingling in the toesThat is a nerve, not a muscle.Wide shoes, less impact, and a GP if it lasts.
Resting the foot completely for weeksThe NHS and Health New Zealand suggest other exercise while it settles.The stage 1 moves.Try: Towel toe curl

Routines to follow

More moves for this area

Questions people ask

Why do my feet hurt when I jump rope?

Skipping lands on the front of your foot about twice a second, at roughly 3 to 5 times your body weight through both feet in lab studies, though the figures vary. The usual triggers are too many minutes too soon, a hard floor and thin or worn shoes. Jump lower, cut the rounds and skip on a forgiving floor.

Why does the ball of my foot hurt after skipping?

The ball of the foot takes the highest pressures in rope jumping. An ache across it is usually metatarsalgia, which the NHS treats with rest, cushioned shoes and soft pads; burning between the toes points to Morton's neuroma.

Why does my arch or heel hurt after jumping rope?

Usually the plantar fascia, the band under the foot, which the NHS links with exercising on hard surfaces. Stretching, taping and cushioned heels help most people, and high-load heel raises can speed the early gains.

Why does the top of my foot hurt after jumping rope?

Tight laces and irritated tendons along the top of the foot are common causes. One spot on a bone that hurts with every landing and later at rest could be a stress fracture: stop jumping and get it checked.

Can jumping rope cause a stress fracture?

No study has reported one, but repeated jumping loads the metatarsals hard, and a sudden increase in activity is the commonest cause of stress fractures. Pain at one spot on a bone needs checking before you skip again.

Is jump rope bad for your feet?

Not when it's built up gradually: rope training improved fitness in trials. Start with short rounds 2 or 3 days a week and add no more than a few minutes a week.

Should I jump rope barefoot or in shoes?

In shoes, especially on a hard floor: shoes slowed how fast each landing built up compared with bare feet. Choose cushioned trainers that fit and leave room for your toes.

What's the best surface for jump rope?

A wooden or sprung floor or a rubber mat rather than concrete, as Health New Zealand and the NHS name hard surfaces among the causes of foot and shin pain. A softer floor helps, but how much you skip matters more.

Can I jump rope with plantar fasciitis?

Usually not while it's flaring: the NHS suggests exercise that doesn't put pressure on your feet, such as swimming. Bring the rope back once first-step pain is settling and heel raises pass the pain rule.

What can I do instead of jump rope?

Cycling, rowing, swimming, the elliptical, step jacks or a fast march keep your heart working without the impact. Our low-impact cardio workout times it for you.

How long will it take?

No one can promise a date. Most foot pain improves within a few weeks, a stress fracture usually takes 6 to 8 weeks to heal, and plantar heel pain can take months.

When should I see a doctor?

Call 999 or go to A&E for a foot that is out of shape or cold and numb after an injury. Get help the same day for a snap or kick at the back of the ankle, a foot you can't walk on, a hot, swollen joint, or any new foot problem if you have diabetes. See a GP if one spot on a bone hurts or it isn't better after 2 weeks; in the US, call 911 where this page says 999.

Related exercise guides

Other pain guides

Sources

  1. Yu 2023 · Shoes, plantar pressure and muscle activity in rope jumping in 10 men (lab study, Int J Environ Res Public Health)
  2. Yu 2022 · Jump rope shoes and leg loads in 10 men (lab study, Bioengineering)
  3. Wu 2026 · Plantar pressure in the speed step in 26 competitive skippers (lab study, Sci Rep)
  4. Lin 2022 · Two-foot and alternate-foot rope jumping in 16 teenage boys (lab study, Children)
  5. Kaewjaratwilai 2025 · Leg loads and muscle activity in barefoot rope jumping in 20 Muay Thai athletes (lab study, Sports)
  6. Li 2023 · Rope skipping barefoot or in shoes in 14 experienced skippers (lab study, Bioengineering)
  7. Bruce 2023 · Joint loads in double-unders, the speed step and running in 16 young competitive skippers (lab study, Sports Biomech)
  8. Buyze 1986 · Six weeks of rope skipping or jogging in 26 inactive adults (training study, Phys Sportsmed)
  9. Singh 2022 · Jump rope training and fitness in young people: 21 studies, 1,021 participants (meta-analysis, J Sports Sci)
  10. Farley 1991 · Preferred hopping frequency in people (lab study, J Appl Physiol)
  11. Warden 2021 · Preventing bone stress injuries in runners with the right workload (review, Curr Osteoporos Rep)
  12. Milgrom 2002 · Metatarsal bone strains in walking and jumping in 2 men (in-body strain gauge study, Foot Ankle Int)
  13. Finestone 2011 · Metatarsal, shin and thigh stress fractures in 76 elite infantry recruits (cohort study, Foot Ankle Int)
  14. Sun 2024 · Risk factors for metatarsal stress fractures in repetitive sport: 32 studies (systematic review, Front Bioeng Biotechnol)
  15. Health New Zealand Te Whatu Ora · Stress fractures of the foot and shin bone
  16. American Academy of Orthopaedic Surgeons (OrthoInfo) · Stress fractures of the foot and ankle
  17. NHS · Pain in the ball of the foot
  18. NHS · Morton's neuroma
  19. Afonso 2023 · Telling the causes of metatarsalgia apart (review, Semin Musculoskelet Radiol)
  20. American Academy of Orthopaedic Surgeons (OrthoInfo) · Sesamoiditis
  21. NHS · Pain in the top of the foot
  22. NHS · Heel pain
  23. NHS · Pain in the bottom of the foot
  24. NHS · Shin splints (past its review date: reviewed February 2023, review due February 2026)
  25. Hoenig 2022 · Bone stress injuries (review, Nat Rev Dis Primers)
  26. O'Malley 1996 · Stress fractures at the base of the second metatarsal in 51 ballet dancers (case series, Foot Ankle Int)
  27. Pitcher 2024 · How well symptoms and examination tests diagnose Morton's neuroma: 9 studies (systematic review, Foot Ankle Orthop)
  28. Hoenig 2023 · Return to sport after low-risk and high-risk bone stress injuries: 76 studies, 2,974 injuries (meta-analysis, Br J Sports Med)
  29. Attia 2021 · Return to sport after a navicular stress fracture: 315 fractures (meta-analysis, Int Orthop)
  30. Hansen 2018 · Plantar fasciitis 5 to 15 years on in 174 patients (cohort study, Orthop J Sports Med)
  31. Biz 2025 · Treating sesamoiditis without surgery: 11 studies, 59 patients (systematic review, Medicina)
  32. Zhou 2025 · Rope speed and ankle movement in 12 elite skippers (lab study, Bioengineering)
  33. NHS · Plantar fasciitis
  34. Ferris 1997 · Leg stiffness on hard and soft surfaces during hopping (lab study, J Appl Physiol)
  35. Garrick 1986 · Injuries in aerobic dance in 411 people (prospective study, Am J Sports Med)
  36. Masterson 2025 · Shoes, bare feet and landing impact in 14 adults (lab study, Sports Biomech)
  37. Ridge 2024 · Shod and barefoot landings in 48 gymnasts, cheerleaders and non-athletes (lab study, PLoS One)
  38. Warden 2021 · Optimal load for low-risk shin and metatarsal bone stress injuries in runners (expert review, J Orthop Sports Phys Ther)
  39. Hähni 2016 · Forefoot cushioning or a metatarsal pad and forefoot pressure in 23 runners (lab study, J Foot Ankle Res)
  40. Kang 2006 · Metatarsal pads, plantar pressure and pain in 13 people with metatarsalgia (prospective study, BMC Musculoskelet Disord)
  41. Kinter 2020 · Instability of the smaller toe joints: diagnosis and treatment without surgery (review, Sports Health)
  42. Thomson 2013 · A steroid injection for Morton's neuroma in 131 people (randomised trial, J Bone Joint Surg Am)
  43. Morrissey 2021 · Managing plantar heel pain: a best practice guide from 51 trials (guide, Br J Sports Med)
  44. Rathleff 2015 · High-load strength training for plantar fasciitis in 48 people (randomised trial, Scand J Med Sci Sports)
  45. Arnett 2002 · Rope jumping and heel bone stiffness in 37 teenage girls (randomised trial, Med Sci Sports Exerc)
  46. Baxter 2021 · Achilles tendon load across rehabilitation exercises in 8 young adults (lab study, Med Sci Sports Exerc)
  47. Silbernagel 2007 · Carrying on with sport using a pain-monitoring model in Achilles tendon pain, 38 people (randomised trial, Am J Sports Med)
  48. Smith 2017 · Should exercises be painful in long-lasting muscle and joint pain? 7 trials, 385 people (meta-analysis, BJSM)
  49. NHS · Heart attack

Exercise education, not a diagnosis or treatment plan. It is written from the guidelines and studies listed above; review by a clinician is pending. If your pain follows an injury, is severe, is getting worse, or comes with any warning sign listed on this page, get it assessed. Health disclaimer.