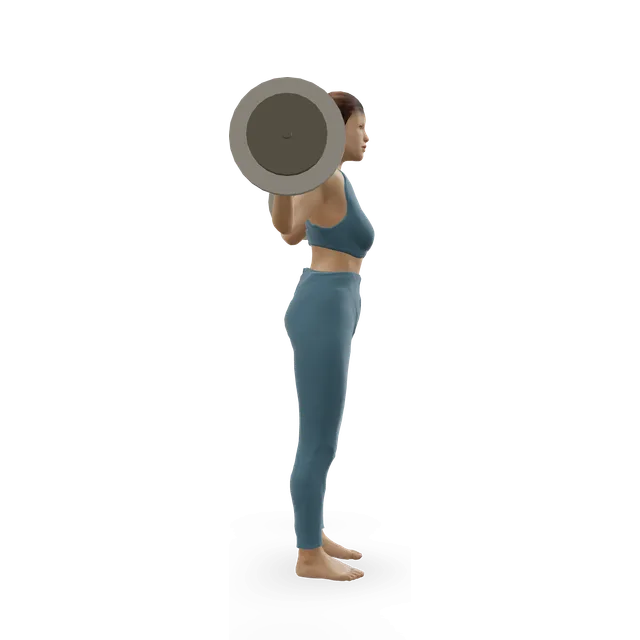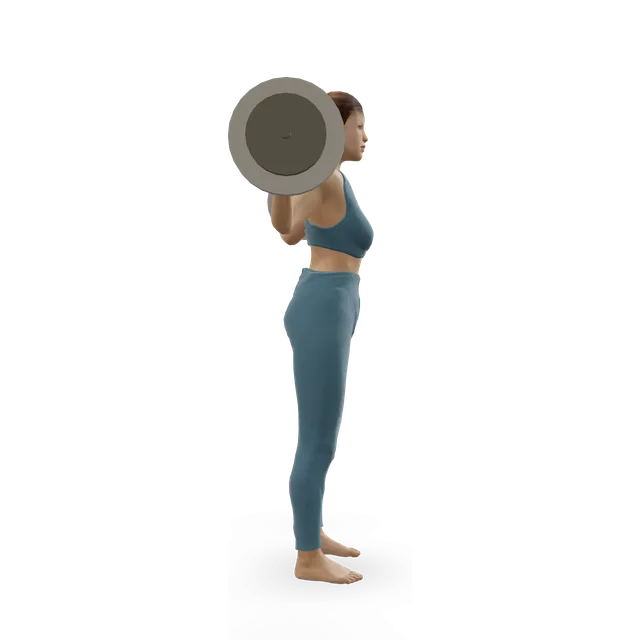Pain guide · Shoulder pain

Shoulder pain when squatting: the low-bar position, the elbows and wrists, mobility and swaps

Shoulder pain when you squat usually comes from holding the bar rather than from the squat itself. In a low-bar squat the bar sits across the back of your shoulders, so they have to turn out and pull back to hold it, and in our reading, a narrow grip, elbows driven up or wrists bent back make your hands, wrists and elbows hold load your back should carry (coaches say so, but nobody has measured it). Where it hurts is the best clue: the front of the shoulder points to the stretched front of the joint or the biceps tendon, the outside with a painful arc to the rotator cuff, the inner elbow to golfer's elbow, and the bony point at the base of the neck to the bar sitting on bone. A higher bar, a wider grip, straight wrists, or a safety squat bar, front or goblet squat usually help, and often the shoulder was first irritated by pressing. No study has measured the shoulders in a squat, so this guide says where each piece of advice comes from.

This guide starts with the signs that need help, from a 999 call for a shoulder that looks out of place after a fall or chest pain that spreads to your arm, neck or jaw, to a same-day check through the National Health Service's 111 line (NHS 111) or a general practitioner (GP) for sudden weakness lifting the arm, a pop at the front of the elbow with bruising, worsening numbness or weakness in the arm, or a hot, swollen shoulder with a fever. It then maps the causes by where it hurts, explains what the studies show about high-bar, low-bar and safety bar squats and why scans often mislead, shows how to change the bar, grip, elbows and wrists today, and gives a three-stage plan with a 3D demo of every move, from goblet squats and rotator cuff work back to your usual squat.

When to get help first

Exercise is for pain that has been checked or is clearly mild and settling.

Get urgent medical help if

  • Call 999 or go to A&E: after a fall or injury, your shoulder looks out of place or has changed shape, you cannot move your arm, or your shoulder is painful, bruised or swollen. Do not drive yourself, and do not try to put it back in yourself.
  • Call 999: shoulder or arm pain with chest pain that feels tight or squeezing, or chest pain that spreads to your arms, neck or jaw, especially with shortness of breath, sweating or feeling sick. It could be a heart attack.
  • Get help from NHS 111: pain or tightness in your chest, neck, shoulders, jaw or arms that comes and goes, often brought on by exercise, stress, emotion or cold and easing after a few minutes' rest. It can be angina, a sign of a heart problem. If you've been diagnosed with angina, get help from NHS 111 too if it feels worse than before, is happening more often, lasts longer or happens when you're resting.
  • Call 999: you suddenly can't fully lift both arms and keep them there, because of weakness or numbness in one arm, especially if one side of your face droops or you slur your words or sound confused. It could be a stroke. Call even if the signs have stopped.
  • Same day (GP or NHS 111): sudden weakness lifting the arm after an injury or fall. A rotator cuff tear caused by an injury needs urgent referral to a shoulder specialist. After a dislocation in anyone over 40, the rotator cuff should be checked: about 40% have a tear.
  • Urgent treatment centre or A&E: a pop or snap and sudden pain during an effort, which could be a torn tendon. At the front of the elbow, with bruising and a bulge in the upper arm, don't wait for it to settle: a torn biceps tendon is best repaired within the first 2 to 3 weeks. If it happened weeks ago, still get it checked: repair is often still possible, though it may need a tendon graft.
  • Same day (GP or NHS 111): a sudden pop or snap with pain at the shoulder or upper arm during a lift, with or without a bulge low in the upper arm. It's usually a torn long head of the biceps. Most need no operation, but the rotator cuff can tear at the same time.
  • Same day (GP or NHS 111): sudden or very bad shoulder pain; you cannot move your arm; the arm or shoulder is badly swollen or has changed shape; pins and needles that do not go away; no feeling in the arm; the arm is hot or cold to the touch; pain that started after an injury such as a fall; or severe pain in both shoulders.
  • Same day: clumsiness in your hands, or numbness, pins and needles or weakness in one or both arms, that is getting worse; problems with balance or walking since the neck pain started; or neck pain with a severe headache.
  • Same day (GP or NHS 111): the shoulder or arm is hot, swollen or red, or you have a high temperature (although not everyone has one) or feel unwell. A joint infection needs same-day care.
  • Same day (urgent GP appointment or NHS 111): a swollen elbow with a very high temperature, or you feel hot, cold or shivery; or severe pain in one joint that started suddenly, swelling around a joint, the skin around a joint has changed colour, or difficulty moving a joint. It could be an infection in the joint or the bursa, or gout.
  • Same day (urgent GP appointment or NHS 111): severe neck pain that starts suddenly or gets worse quickly; heaviness or weakness in the arms or legs; pins and needles in an arm along with neck or arm pain; or pain between the shoulder blades.

See a doctor or physiotherapist if

  • Pain that is getting worse or has not improved after 2 weeks of looking after it yourself, or it is very hard to move your arm. In many areas you can refer yourself to physiotherapy.
  • Your shoulder has partly or fully come out of joint, or you worry it might.
  • Pins and needles or a cold arm alongside neck pain, or a new loss of strength or feeling in the arm that you cannot explain (a possible nerve problem).
  • Painful clicking or snapping at the front of the shoulder, or a feeling of something slipping there. The tendon can slip out of its groove, usually alongside a rotator cuff tear, so ask for an assessment.
  • Not improving after a good 3 months of exercise, or the arm is clearly weak: ask for a specialist opinion.
  • Pain on top of the shoulder with no injury that hasn't eased after 6 to 12 weeks of changing your training: ask a GP or physiotherapist for an assessment.
  • Elbow or arm pain that hasn't gone after a few weeks of looking after it yourself (for tennis elbow, the NHS says after at least 2 weeks of self-care). In many areas you can refer yourself to NHS physiotherapy.
  • Pins and needles that keep coming back or are constant, numbness in the ring and little fingers that doesn't go, a weak or clumsy hand, or visible wasting between the thumb and index finger. Ask about referral: one NHS referral guide treats permanent numbness or wasting as urgent.
  • Not improved after 2 weeks of looking after it at home, getting worse, keeps coming back, or stopping you doing normal activities. In many areas you can refer yourself to NHS physiotherapy.
  • A past history of cancer, an unexplained lump or swelling, weight loss, or pain that is constant and does not ease when you change position.
  • See a GP if you have pain and stiffness for more than a week, especially if you're over 50, it's in both shoulders (often the neck and hips too) and the stiffness lasts longer than 45 minutes in the morning. It can be polymyalgia rheumatica.

Where does it hurt?

Location narrows the likely causes; it does not diagnose.

Chest pain that feels tight or squeezing, or spreads to an arm, neck or jaw

Call 999, even mid-set: it could be your heart. Don't wait to see if it passes.

Deep at the front of the shoulder as you set the bar, worse with a low bar or a narrow grip

Often the front of the joint stretched as the shoulder turns out to hold the bar, or the biceps tendon (our reading). A higher bar and a wider grip usually help.

Read: Front of shoulder pain →
The outside of the shoulder and upper arm, with a painful arc lifting the arm and soreness lying on it

Rotator cuff related pain, often called impingement. Pressing often starts it, and exercise is the treatment.

Read: Shoulder impingement (rotator cuff pain) →
A clunk, a slipping feeling or a dead arm in the bar position

A shoulder that partly slips (instability). Leave the low bar out and get it assessed.

Read: Shoulder dislocation and instability →
On top of the shoulder at the end of the collarbone, where one finger can point to it

The AC joint (acromioclavicular joint), often also sore with bench pressing and dips. A higher bar or a safety squat bar usually helps.

Read: AC joint injury and pain →
The back of the shoulder or around the shoulder blade, after squat days

Often the upper back and rear shoulder muscles holding the bar (our reading); soreness fades within days.

Read: Back of shoulder pain →
The inner elbow and forearm, worse gripping, after low-bar sessions

Often golfer's elbow (medial epicondylitis). Coaches blame a narrow grip with the wrists bent back and the elbows driven up, so the forearm holds load the back should carry: our reading, not measured. Widen your grip, keep your wrists straight and let your elbows point down.

Read: Golfer's elbow →
The outer elbow, worse gripping

Often tennis elbow; the same grip changes help.

Read: Tennis elbow →
A sudden pop at the front of the elbow, then bruising and a bulge in the upper arm

Possibly a torn biceps tendon: get it checked the same day, as the warning signs say. Repair does better early.

Read: Front of the elbow (biceps tendon) →
Pins and needles or numbness in the ring and little fingers, worse with the elbow bent

The ulnar nerve at the elbow (our reading of the position). Stop what brings it on.

Read: Ulnar nerve entrapment →
The back of the wrist, bent back under the bar

The wrist holding load the back should carry. Straight wrists and a wider grip usually help; our wrist lifting guide covers the rest.

Read: Wrist pain when lifting weights →
The wrists in the front squat rack

Our front squat wrist guide covers the rack, crossed arms and straps.

Read: Wrist pain in front squats →
The bony point at the base of the neck where the bar sits

The bar sitting on bone: move it onto the muscle of your upper back. Very rarely, a crack and sharp pain between the shoulder blades is a small fracture of that bony point, which needs checking.

Read: Neck pain after a workout →
The neck, the top of the shoulder blade and down the arm, with pins and needles

A nerve in the neck, which changes with neck movement.

Read: Pinched nerve in the neck →
The same shoulder pain bench pressing or pressing overhead

The same causes, often started by pressing. Our press guides cover the grip, range and a plan back.

Read: Shoulder pain when benching →

Understand it

What holding the bar asks of the shoulders, and what no study has countedEmerging evidence

In a high-bar squat the bar rests on the muscle of the upper back just below the neck; in a low-bar squat it sits a few centimetres lower, across the back of the shoulders. A review of lab studies found the low bar leans the trunk further forward and works the hips and back harder, while the high bar keeps you more upright with more knee bend; one small study of 12 trained men found the opposite pattern of knee and hip bend, so the details are mixed. The low bar usually lets people lift the most.

To keep the bar on that shelf, the shoulders turn out and pull back with the elbows behind the bar, much like a milder version of the arm-up-and-back "high-five" position that went with signs of a shoulder that might slip in 159 weight trainers. In our reading of coaching sources and our squat guide, a narrow grip, elbows driven up or wrists bent back make the hands, wrists and elbows hold load the back should carry. Nobody has measured any of this: no study has counted shoulder, elbow or wrist pain from squats, or measured the shoulders, elbows or wrists in a back squat.

Sources 1, 2, 3, 4, 5

Who gets itEmerging evidence

Often the squat shows up a shoulder that pressing has already irritated. In 104 Swedish powerlifters, a current shoulder injury was strongly linked with starting during bench press training (9 of 16 current shoulder injuries started there). In powerlifting, the commonest injury sites were the lower back (30.8%), the shoulder (19.6%) and the elbow and upper arm (8.0%), at 1.0 to 4.4 injuries per 1,000 hours of training, which is low next to team sports.

Up to 36% of resistance training injuries were at the shoulder in one review; shoulder, elbow and hand or wrist injuries were more common in powerlifters over 40; and a scoping review found shoulder instability and overuse the commonest shoulder injuries in weightlifting. In US emergency departments, the shoulder was a third of upper limb weightlifting injuries, mostly from drops and crushes rather than holding a bar. No study gives the share of each cause in people who squat.

Sources 6, 7, 8, 9, 10, 11, 12

The elbows: golfer's elbow and a torn biceps tendonEmerging evidence

Golfer's elbow (medial epicondylitis) is pain where the forearm muscles attach to the inner elbow. It makes up about 10% of elbow tendon diagnoses, is commonest from 40, is diagnosed by examination, and is treated without surgery first; surgery is considered only after 6 to 12 months of other care. Other causes of inner elbow pain include the ulnar nerve and the inner elbow ligament.

A torn biceps tendon at the elbow is different: often a pop, then bruising, a bulge in the upper arm and weakness turning the palm up. It's commonest in men over 30, and in people who smoke or use steroids. Surgery to reattach the tendon is needed for full strength, and in 183 strength athletes who had it repaired, all returned to sport, while a longer delay before surgery went with worse results. Deadlifts and curls, not squats, were the commonest lifting causes.

Sources 13, 14, 15, 16

The neck under the barEmerging evidence

The bar should sit on muscle, never on the bones of the neck. A review of case reports describes rare fractures of the bony points at the base of the neck (C6 to T1) in weightlifters, from a blow or a hard muscle pull, felt as a crack and sharp pain between the shoulder blades that usually settles over weeks. They are often missed at first, so a crack with sharp pain is worth checking.

Source 17

When a scan helps, and what it can't tell youStrong evidence

Not at first for rotator cuff, AC joint or elbow tendon pain. In 96 shoulders without symptoms, a magnetic resonance imaging (MRI) scan showed a rotator cuff tear in 34%, rising to 54% over 60, and golfer's elbow is a clinical diagnosis with an ultrasound or MRI only when the diagnosis is unsure.

Scans matter for a suspected biceps tear at the elbow (an ultrasound or MRI can confirm it, though an obvious tear may not need one), sudden weakness after an injury, a shoulder that has slipped, a crack between the shoulder blades and worsening nerve signs. The NHS says a health professional may send you for tests such as an X-ray to check the cause.

Sources 18, 13, 15, 19

How it usually goesEmerging evidence

No study follows shoulder pain from squats. In the largest rotator cuff trial (708 adults), shoulder pain and function improved substantially over a year in every group. The NHS says shoulder pain usually needs 2 weeks of looking after before it starts to ease, and can take 6 months or longer. Most injured powerlifters kept training with changes: only 16% of those currently injured had stopped completely. No one can promise a date.

Sources 20, 19, 13, 6

What helps, and how strong the evidence is

Exercise is the first treatment for rotator cuff painStrong evidence

In the GRASP trial of 708 adults with rotator cuff pain, up to six physiotherapy sessions of progressive exercise did no better over a year than one session of advice with a home exercise programme, and every group improved; a steroid injection helped at 8 weeks but not over 12 months. In 102 people waiting for surgery, specific rotator cuff and shoulder blade exercises gave 24 points of improvement against 9 on a shoulder score, 69% against 24% reported a good result, and fewer chose surgery (20% against 63%).

Weight trainers who trained their external rotators (the muscles that turn the arm out) showed fewer signs of impingement and of a shoulder that might slip, though a snapshot study can't show which came first.

Sources 20, 21, 5, 22

The high bar, the safety squat bar and the front squatEmerging evidence

The high bar keeps you more upright than the low bar. A safety squat bar, held by handles in front, cut the trunk's lean by about 7 degrees and the load lifted by about 11% in 12 powerlifters, bent the hip less with similar knee demand and about 5% less load in 15 men, and worked the leg muscles about as hard at the same relative load in 32 men. The front squat worked the muscles about as hard as the back squat with less compression in the knee in 15 trained adults.

None of these studies measured the shoulders. That the safety squat bar spares them is our reading, because the hands hold handles in front and the shoulders don't have to turn out to hold a bar behind you.

Sources 1, 23, 24, 25, 3, 26

Golfer's elbow: loading helps, but the evidence is thinEmerging evidence

Across 5 studies of 143 people, eccentric exercise (slow lowering) for the forearm muscles eased pain and improved function in medial epicondylitis, but only one trial showed it beat another treatment, and certainty is low. A UK review puts rest from the aggravating load, physiotherapy and graduated strengthening first. Our golfer's elbow guide has the plan.

Sources 27, 13

A torn biceps tendon at the elbow: repair, and sooner rather than laterEmerging evidence

Orthopaedic surgeons advise surgery to reattach the tendon to regain full strength, with non-surgical care an option for some older or less active people. In 183 strength athletes after repair, 73% regained full strength and 15% had a complication, including 3% that tore again, and a longer wait before surgery went with worse scores. This is a case series without a comparison group.

Sources 15, 16

How much pain is OK while you exercise?

Up to about 5 out of 10 for the shoulder, 3 to 4 for the elbow, settled by the next sessionEmerging evidence

This guide uses the shoulder hub's rule, as our other shoulder guides do. During shoulder strengthening, pain up to about 5 out of 10 is acceptable, and a little is expected. By your next session it should be back to where it was before. If it isn't, use a lighter band or weight or a smaller range next time, not nothing. It is how the Holmgren trial set each person's load.

For the elbow, the elbow hub's stricter rule applies. Some discomfort during forearm exercises is fine. Keep it mild: no more than about 3 to 4 out of 10. It should settle within an hour or so, and your elbow should be no worse the next morning. If it is worse, go lighter next time (a lighter weight, a bendier bar, fewer reps or a shorter hold), not nothing. Tingling is the exception: stop anything that brings on pins and needles in your hand, especially in the ring and little fingers.

For squats (our suggestion, built on these rules): judge each set by its last reps, and use the bar position (goblet, safety bar, high bar, low bar), the grip width and the load where your shoulder stays at 5 out of 10 or less (your elbow at 3 to 4) and is back to its usual level by the next session. A catch, a clunk or a feeling of slipping in the bar position, pins and needles in the hand, a pop with bruising, or any warning sign isn't a pain-rule question.

Source 21

The exercise plan: 3 stages

Start at the first stage. Each move opens a full guide with a 3D demo.

Stage 1

Keep squatting, take the bar off your back

About weeks 0 to 2, legs 2 or 3 times a week and shoulder work 3 to 5 days a week: keep the legs training with no bar on the shoulders, and start the rotator cuff and upper back work. No low-bar or high-bar squats for now. Doses are editorial unless a source is named.

Dumbbell goblet squat demonstrated on the 3D figure3D demoDumbbell goblet squatIntermediate · A dumbbell

3 or 4 sets of 8 to 12, stopping about 2 reps short of failure, elbows down and the weight close · Editorial, as in our squat plans

Easier: Bodyweight squat · Harder: Barbell front squat

Leg press demonstrated on the 3D figure3D demoLeg pressBeginner · Strength machine

3 sets of 10 to 12 · Editorial: heavy leg work with no bar on the shoulders

Harder: Bodyweight squat

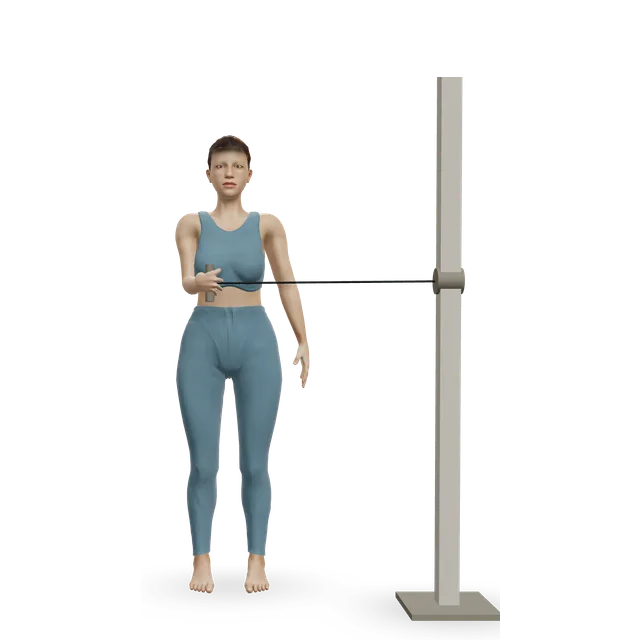
Standing band external rotation demonstrated on the 3D figure3D demoStanding band external rotationBeginner · A band + An anchor point

3 sets of 15, light band, slow return, elbow at your side · The Holmgren trial's rotator cuff exercises used 3 sets of 15, twice a day for 8 weeks, with pain kept at 5 out of 10 or less, as our bench press shoulder guide does

Easier: Stick-assisted external rotation (lying) · Harder: Side-lying external rotation

Band row demonstrated on the 3D figure3D demoBand rowBeginner · A band + An anchor point

3 sets of 10 to 15, stopping 2 to 3 reps short of failure · The move page's dose

Harder: Supported single-arm dumbbell row

Side-lying open book demonstrated on the 3D figure3D demoSide-lying open bookBeginner · No equipment

8 to 10 slow openings each side, pausing 2 seconds at the end · The move page's dose

Harder: Thoracic rotation

Scapular push-up (push-up plus) demonstrated on the 3D figure3D demoScapular push-up (push-up plus)Beginner · No equipment

2 or 3 sets of 10, on a wall or bench first · As in our bench press shoulder guide (editorial)

Easier: Dumbbell shoulder-blade punch · Harder: Push-up

Move on when: Goblet squats and the shoulder work pass the pain rule, and your shoulder is back to its usual level by the next session, for a week (editorial).

Follow along: a timer, a cue and the next move, one step at a time.
Stage 2

Bring the bar back, high and wide

About weeks 2 to 6: a barbell squat with the bar high and the grip wide, stronger external rotators and upper back, and the bar position you use coming back a notch at a time. If the high bar still hurts, use a safety squat bar or a front squat with crossed arms or straps for a while (written swaps).

Olympic squat (high-bar back squat) demonstrated on the 3D figure3D demoOlympic squat (high-bar back squat)Advanced · A barbell

3 sets of 5 to 8 at about half your old working weight, grip wide, wrists straight, elbows down · Editorial. The high-bar back squat

Easier: Bodyweight squat

Side-lying external rotation demonstrated on the 3D figure3D demoSide-lying external rotationBeginner · A dumbbell

3 sets of 15, lowering over about 3 s · The Holmgren trial's sets and reps (twice a day for 8 weeks, then once a day to week 12), as our bench press shoulder guide uses them; the 3 s lowering is editorial

Easier: Standing band external rotation · Harder: Cuban rotation

Face pull demonstrated on the 3D figure3D demoFace pullIntermediate · A band

3 sets of 12 to 15 · As in our bench press shoulder guide (editorial)

Easier: Prone Y-T-W raises · Harder: Tuck back lever

Chest-supported dumbbell row demonstrated on the 3D figure3D demoChest-supported dumbbell rowBeginner · A dumbbell + A bench or box

3 sets of 8 to 12 · As in our bench press shoulder guide (editorial)

Harder: Supported single-arm dumbbell row

Shoulder dislocates with a strap (pass-throughs) demonstrated on the 3D figure3D demoShoulder dislocates with a strap (pass-throughs)Beginner · Other / check instructions

2 sets of 10 slow passes, with a wide grip, only in a range that stays pain-free · The move page's dose. Stop if it brings on a clunk or a slipping feeling

Easier: Overhead stick stretch · Harder: Prone swimmers

Barbell front squat demonstrated on the 3D figure3D demoBarbell front squatAdvanced · A barbell

3 sets of 5 with crossed arms or straps, safety pins set · Editorial, as in our front squat technique workout's grip block. Optional: a squat with no bar on your back

Easier: Bodyweight squat · Harder: Overhead squat

Move on when: High-bar squats at about your old working weight pass the pain rule for a week, and side-lying external rotation is comfortable for 3 sets of 15 with a heavier weight (editorial).

Follow along: a timer, a cue and the next move, one step at a time.
Stage 3

Back to your usual squat

From about week 6: your usual bar position and load, one change at a time by the written steps below. No study has tested a return to the squat after shoulder pain, so the order is editorial.

Barbell back squat demonstrated on the 3D figure3D demoBarbell back squatAdvanced · A barbell

Your usual bar position (the low bar if you use it), with your grip wider than before, from about half your old working weight, adding 5% to 10% every week or two while the shoulder passes the rule · Our suggestion, using the 2% to 10% steps the American College of Sports Medicine gives healthy adults; no trial has tested it

Easier: Bodyweight squat · Harder: Overhead squat

Olympic squat (high-bar back squat) demonstrated on the 3D figure3D demoOlympic squat (high-bar back squat)Advanced · A barbell

Your usual sets, on days the low bar complains · Editorial

Easier: Bodyweight squat

Cable external rotation demonstrated on the 3D figure3D demoCable external rotationBeginner · A cable machine

3 sets of 10 to 12, heavier than in stage 2 · As in our bench press shoulder guide (editorial)

Harder: Side-lying external rotation

Face pull demonstrated on the 3D figure3D demoFace pullIntermediate · A band

3 sets of 12 to 15, twice a week, kept up · Editorial

Easier: Prone Y-T-W raises · Harder: Tuck back lever

Move on when: Your usual squat sessions pass the pain rule for 2 weeks. Keep rotator cuff and upper back work twice a week; if a session flares it, go back a stage for a few days, not to nothing (editorial).

Follow along: a timer, a cue and the next move, one step at a time.

What to change for now

Change the bar, grip, elbows and wrists (written steps)

Our 3D figure can't show these changes. They come from our squat guide, coaching advice and lab studies of bars; where a step is our reading or suggestion, it says so. No trial has tested a change to the squat for shoulder, elbow or wrist pain.

  • 1. Bar position: move the bar up onto the muscle of your upper back (a high-bar squat) while it's sore. The high bar keeps you more upright, and the bar position is a choice, not a rule.
  • 2. Grip: hold just outside your shoulders or wider, and squeeze the bar into your back so your back carries it, not your hands. If a low bar hurts your wrists or elbows, widen your grip and keep your wrists straight, as our squat guide says.
  • 3. Elbows and wrists: let your elbows point down and slightly back rather than up behind you, with your wrists straight in line with your forearms (coaching advice; not measured).
  • 4. Neck: the bar sits on muscle, never on the bones of your neck.
  • 5. Swaps: a safety squat bar (more upright, about 5% to 11% less load, the legs worked about as hard; that it spares the shoulders is our reading), a front squat with crossed arms or straps, a goblet squat, a belt squat or the leg press.
  • 6. Load: about half your old working weight, adding 5% to 10% while the shoulder passes the pain rule (our suggestion, using the American College of Sports Medicine's 2% to 10% steps for healthy adults).
  • 7. Order: squat before heavy pressing, or press on another day, while it's sore (our suggestion).

Sources 1, 3, 23, 24, 25, 26, 29

Everyday life and sport (written steps)

The NHS's self-care advice is to keep the shoulder moving, not to stop using it completely, and not to make up your own strenuous exercises or use heavy gym equipment while it hurts; that is why the first stage keeps the bar off your shoulders and loads them only with light bands (our reading). The rest are our suggestions.

  • 1. Keep the arm moving through the day, using painkillers if you need them to keep moving, as the NHS suggests.
  • 2. Reaching overhead, carrying and lifting at work: keep loads close and below shoulder height while it's sore; if night pain bothers you, lie on the other side or rest the arm on a pillow.
  • 3. Bench and overhead pressing: if pressing started it, change those first using our press guides, because most powerlifters' shoulder injuries started in bench press training.
  • 4. Powerlifting: the low bar comes back last, and your usual narrow grip only once a wider grip has passed the rule for 2 weeks; train with a safety squat bar or the high bar in the meantime.
  • 5. Team sports, climbing and throwing: once your usual squat and pressing pass the rule, build up contact, overhead and throwing work over a few weeks.

Sources 19, 6

Positions to swap, and why

Habit or positionWhy it mattersInstead
Low-bar squats while it's soreHolding the low bar turns the shoulders out and back, and the low bar leans you forward (the shoulder demand is our reading).A high-bar squat, or a safety squat bar.Try: Olympic squat (high-bar back squat)
A narrow gripCoaching sites name it a common cause, and our squat guide says widen the grip if your wrists or elbows hurt.Grip just outside your shoulders or wider.
Wrists bent back, the bar in your fingersYour hands and wrists then hold load your back should carry (our squat guide).Straight wrists, and squeeze the bar into your back.
Elbows driven up behind youCoaches say it turns the shoulders further and loads the wrists; nobody has measured it.Elbows down and slightly back.
The bar on the bones of your neckIt should sit on muscle; very rarely, the bony point there can fracture in lifters.The bar on the muscle of your upper back, or a safety squat bar.
Behind-the-neck presses and pulldownsIn weight trainers, these lifts went with signs of a shoulder that might slip.Press and pull in front of your head.Try: Face pull
Heavy pressing before squats on the same dayA shoulder already sore from pressing is a common start (the order is our suggestion).Squat first, or press on another day.
Stretching or rolling through pain to open up the shoulderNo study tests it as a fix; pain in the bar position is a signal, not a mobility target (editorial).Rotator cuff and upper back strength work.Try: Standing band external rotation
Resting the arm completelyThe NHS says not to stop using your shoulder completely, as it can stop it getting better.Gentle movement and the first-stage moves.Try: Band row
Training through tingling in your handThat is a nerve: the elbow hub's rule says stop anything that brings it on.Leg work with no bar, and see a GP if it lasts.Try: Dumbbell goblet squat

Routines to follow

More moves for this area

Questions people ask

Why does my shoulder hurt when I squat?

Usually the bar position: a low bar, a narrow grip or wrists bent back make your shoulders turn out and your hands hold load your back should carry (our reading of coaching advice; nobody has measured it). Often the shoulder was already sore from pressing. Move the bar higher, widen your grip and keep your wrists straight.

Why do low-bar squats hurt my shoulders?

The low bar sits across the back of your shoulders, so they have to turn out and pull back to hold it. If it hurts, a wider grip or the high bar usually helps, and the low bar can come back last.

Why does my elbow hurt when I squat?

Usually the inner elbow, golfer's elbow, from gripping a low bar with the wrists bent back and the elbows driven up (coaching opinion). Widen your grip, keep your wrists straight and let your elbows point down. A pop at the front of the elbow with bruising is different and needs a same-day check.

Why do my wrists hurt when I back squat?

The bar has usually slid into your fingers and your wrists are bending back to hold it. Squeeze the bar into your back with straight wrists and a wider grip, and see our wrist lifting guide if it lasts.

Should I switch to high-bar squats?

For a while, if the low bar hurts: the high bar keeps you more upright and asks less of the shoulders. Both build strength, and the low bar usually lifts a little more.

Is a safety squat bar better for shoulder pain?

It takes your hands off the bar behind you, keeps you more upright and still works your legs about as hard at the same relative load. No study has measured the shoulders with it, so sparing them is our reading, but it's the usual swap.

How wide should my grip be?

Wide enough that your wrists stay straight and your shoulders don't ache: just outside your shoulders or wider while it's sore. No study has tested grip width in the squat.

The bar hurts the bone at the base of my neck. Is that normal?

No: the bar should sit on the muscle of your upper back, never on the bones of your neck. A sudden crack and sharp pain between the shoulder blades needs checking; very rarely it's a small fracture of that bony point.

Can I squat with rotator cuff pain?

Usually, yes, with the bar higher, a wider grip, a safety squat bar or a goblet squat. Keep up rotator cuff exercises alongside, because exercise is the main treatment for rotator cuff pain.

Do I need a scan?

Not at first: tears show on scans of many shoulders that don't hurt. A pop with bruising, sudden weakness after an injury, a shoulder that slipped or worsening nerve signs need prompt assessment.

How long will it take?

No one can promise a date. The NHS says shoulder pain usually needs 2 weeks of looking after before it eases, and can take 6 months or longer.

When should I see a doctor?

Call 999 if your shoulder looks out of place after a fall, or for chest pain that feels tight or spreads to your arm, neck or jaw. Get help the same day for sudden weakness lifting the arm, a pop at the elbow with bruising, worsening numbness or weakness in the arm, or a hot, swollen shoulder with a fever, and see a GP if it isn't better after 2 weeks. In the US, call 911 where this page says 999.

Related exercise guides

Other pain guides

Sources

  1. Glassbrook 2017 · The biomechanical differences between high-bar and low-bar back squats (narrative review, J Strength Cond Res)
  2. Glassbrook 2019 · High-bar and low-bar back squats up to a 1RM, in 18 men (lab study, J Strength Cond Res)
  3. Kristiansen 2021 · Safety bar, high-bar and low-bar squats compared, in 14 recreationally trained adults (lab study, Int J Environ Res Public Health)
  4. van den Tillaar 2020 · Low and high bar placement in 6RM squats, in 12 trained men (lab study, J Hum Kinet)
  5. Kolber 2013 · Signs of anterior shoulder instability and laxity in weight trainers, in 159 men (case-control study, J Strength Cond Res)
  6. Strömbäck 2018 · Injuries in 104 Swedish classic powerlifters (cross-sectional survey, Orthop J Sports Med)
  7. Tung 2024 · Injuries in weightlifting and powerlifting, 17 reports (updated systematic review, BMJ Open Sport Exerc Med)
  8. Keogh 2017 · The epidemiology of injuries across the weight-training sports (systematic review, Sports Med)
  9. Kolber 2010 · Shoulder injuries attributed to resistance training (review, J Strength Cond Res)
  10. Siewe 2011 · Injuries and overuse problems in 245 powerlifters (questionnaire, Int J Sports Med)
  11. Daher 2025 · Shoulder injuries in weightlifting athletes (scoping review, Shoulder Elbow)
  12. Lee 2026 · Upper limb weightlifting injuries in US emergency departments, 3,189 cases (surveillance study, Orthop J Sports Med)
  13. Tahir 2026 · Medial epicondylitis (golfer's elbow): presentation, diagnosis and management in the UK (review, Cureus)
  14. Adani 2025 · Causes, diagnosis and treatment of non-traumatic inner elbow pain (review, Cureus)
  15. AAOS OrthoInfo · Biceps tendon tear at the elbow
  16. Lappen 2025 · Distal biceps tendon repair in 183 competitive strength athletes (case series, Orthop J Sports Med)
  17. Boutros 2025 · Clay shoveler's fracture, a fracture of a spinous process at the base of the neck (review, Spine Surg Relat Res)
  18. Sher 1995 · Rotator cuff tears on MRI in 96 shoulders without symptoms (imaging study, J Bone Joint Surg Am)
  19. NHS · Shoulder pain (past its review date: reviewed May 2023, review due May 2026)
  20. Hopewell 2021 · Progressive exercise vs best practice advice, with or without a steroid injection, for rotator cuff disorders in 708 adults: GRASP (randomised trial, Lancet)
  21. Holmgren 2012 · A specific exercise strategy and the need for surgery in shoulder impingement, in 102 people (randomised trial, BMJ)
  22. Kolber 2014 · Signs of shoulder impingement in recreational weight trainers, in 77 men (case-control study, J Strength Cond Res)
  23. Hecker 2019 · The safety squat bar and trunk and leg mechanics, in 12 powerlifters (lab study, J Strength Cond Res)
  24. Johansson 2024 · The safety squat bar against a standard bar back squat, in 15 men (lab study, J Strength Cond Res)
  25. Vantrease 2021 · Strength, muscle activity and bar speed with a traditional or safety squat bar, in 32 men (randomised crossover, J Strength Cond Res)
  26. Gullett 2009 · Back and front squats compared, in 15 trained adults (lab study, J Strength Cond Res)
  27. See 2026 · Eccentric exercise for medial epicondylitis, 5 studies of 143 people (systematic review, Complement Ther Med)
  28. NHS · Heart attack
  29. ACSM 2009 · Progression models in resistance training for healthy adults (position stand, Med Sci Sports Exerc)

Exercise education, not a diagnosis or treatment plan. It is written from the guidelines and studies listed above; review by a clinician is pending. If your pain follows an injury, is severe, is getting worse, or comes with any warning sign listed on this page, get it assessed. Health disclaimer.